fbpx

Please wait...


BLOG

No more posts

Not all flat feet are a problem. In fact, many people who believe they have flat feet have perfectly normal, healthy feet that require no treatment whatsoever.

At Dubai Podiatry Centre, one of the most important parts of assessing flat feet is understanding why the arch appears low.

There are several different types of flat feet, and the treatment, if any is required, depends on the structure, flexibility and alignment of the foot and ankle.

1. Some Feet Are Naturally Flat and Perfectly Healthy

Feet come in many different shapes and structures.

Some people naturally have high arches, while others have lower arches. Both can be completely normal.

One particularly interesting difference is the amount of natural fibrofatty padding underneath the foot.

The Importance of Natural Foot Padding

The sole of the foot contains specialised fibrofatty tissue that cushions the bones and helps absorb pressure when we stand and walk.

The amount and distribution of this padding varies between individuals, influenced by genetics, age and other factors.

Some people have generous natural padding underneath their feet, making the arch appear lower than it actually is.

Others have less visible soft tissue padding, making their feet look more bony and highly arched.

A well padded foot may therefore look flat even when the underlying arch structure is perfectly normal.

This is not necessarily related to obesity, and it does not mean the foot requires correction.

In fact, natural plantar cushioning can be particularly beneficial as we get older, when loss or displacement of the protective fat pads may cause discomfort beneath the bones of the feet.

The important message is simple: a foot that looks flat is not necessarily a structurally flat foot.

2. How Do We Know Whether a Foot Is Really Flat?

At Dubai Podiatry Centre, we examine the foot in several positions.

We look at the foot when the patient is sitting, standing and rising onto their tiptoes.

We assess three important factors:

Arch formation: Is there a well formed medial arch when the foot is not bearing weight?

Flexibility: Does the arch reappear when the patient stands on tiptoes, and can the foot be repositioned comfortably?

Ankle alignment: Does the ankle or heel lean inwards when the patient stands?

These observations help distinguish a naturally low arch, a flexible flat foot and a rigid flat foot.
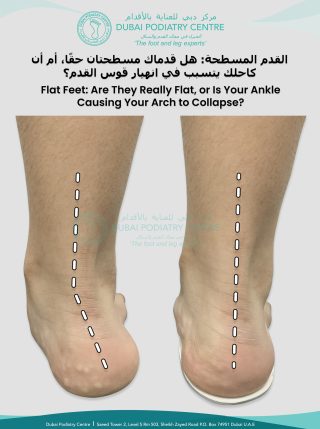
Rear view comparing ankle and heel alignment, illustrating how inward ankle lean can contribute to a lowered foot arch3. The Hyperpronated Foot: When the Ankle Collapses Inwards

One of the common patterns we assess is excessive pronation, also known as hyperpronation.

This is particularly interesting because the patient may have a beautifully formed arch when sitting.

However, when they stand, the arch lowers significantly.

Why Does This Happen?

When the foot bears weight, the heel may tilt outwards and the ankle region may appear to lean inwards.

This movement is often accompanied by lowering of the medial longitudinal arch.

In other words, the arch is present when the foot is unloaded, but it becomes much flatter when the patient stands.

This is a flexible flatfoot pattern associated with excessive pronation.

Pronation is a normal and necessary movement during walking. It becomes clinically relevant when the amount or timing of movement contributes to symptoms, instability or excessive mechanical loading.

Not every hyperpronated foot requires treatment. We consider the patient’s symptoms, age, mobility, function and overall alignment before recommending intervention.

4. What About Ligamentous Laxity?

Some people have naturally more flexible ligaments and joints.

This is known as ligamentous laxity or joint hypermobility.

In these individuals, the arches may lower more easily during standing.

We may also observe increased movement elsewhere in the body, such as hyperextension of the knees, increased flexibility of the ankles, greater movement through the hips and pelvis, and generalised joint hypermobility.

Ligamentous laxity can contribute to flexible flat feet, although it is not present in every patient with low arches.

A full assessment helps us understand whether the flexibility is normal for that individual or is contributing to pain and instability.

5. Flexible Flat Feet Versus Rigid Flat Feet

This is one of the most important distinctions when assessing foot structure.

Flexible Flat Feet

A flexible flat foot typically has an arch when sitting or when the foot is not bearing weight.

When standing, the arch lowers.

When the patient rises onto their tiptoes, the arch may reappear.

The foot can usually be repositioned without significant restriction.

Where excessive pronation is contributing to symptoms or functional problems, corrective orthotic therapy may be considered.

Rigid Flat Feet

A rigid flat foot remains flat even when the foot is not bearing weight.

The arch does not reappear normally when the patient rises onto their tiptoes, and the foot may have restricted movement.

Possible causes include arthritis affecting the joints of the foot, structural changes to the bones or joints, tarsal coalition, long standing deformity and advanced adult acquired flatfoot deformity.

Rigid flat feet require careful assessment. Imaging or specialist referral may be necessary, particularly when pain, progressive deformity or restricted movement is present.

6. Corrective Orthotics: Supporting a Flexible Foot in Better Alignment

At Dubai Podiatry Centre, we distinguish between two important categories of custom made orthotics: corrective and accommodative.

They are not the same, and they serve different purposes.

Corrective orthotics are designed to influence the position and mechanics of a flexible foot and ankle.

For example, a patient may have a well formed arch when sitting, but the arch lowers excessively when standing because of hyperpronation.

When clinically appropriate, a corrective orthotic can be designed using the foot’s non weightbearing shape and its assessed alignment.

The orthotic is then manufactured with specific contours and posting angles intended to improve support and influence how the foot and ankle function during weightbearing.

How Corrective Orthotic Therapy Works

At Dubai Podiatry Centre, our approach includes:

1. Examining the patient’s foot and ankle alignment
2. Assessing the shape of the foot without weightbearing
3. Determining how much of the pronation is flexible and correctable
4. Designing a custom orthotic with the appropriate arch support and alignment features
5. Introducing the orthotic gradually, according to the patient’s tolerance and treatment plan
6. Monitoring comfort, symptoms and foot function over time

The aim is to reduce excessive mechanical loading and improve functional alignment.

Corrective orthotics are individualised and may require adjustments as the patient’s symptoms, footwear, activity or foot mechanics change.

However, wearing corrective orthotics does not necessarily permanently reshape the foot or ankle. Their principal mechanical effect occurs while they are being worn.

7. Accommodative Orthotics: Supporting the Foot Without Forcing Correction

Accommodative orthotics are also custom made, but they have a different purpose.

Rather than attempting to reposition a foot into a new alignment, they are designed to fit and support its existing structure.

These orthotics are particularly useful when the foot cannot comfortably be moved into a neutral position.

Examples include rigid flat feet, arthritic feet with restricted joint movement, structural bone or joint deformities, feet with painful pressure points and certain complex or sensitive foot conditions.

An accommodative orthotic can distribute pressure more evenly, provide cushioning and support the foot in a comfortable position.

It does not attempt to force a rigid or arthritic foot into an alignment that the joints cannot achieve.

These orthotics may be used for many years, although they require periodic assessment and replacement as materials wear or the patient’s needs change.
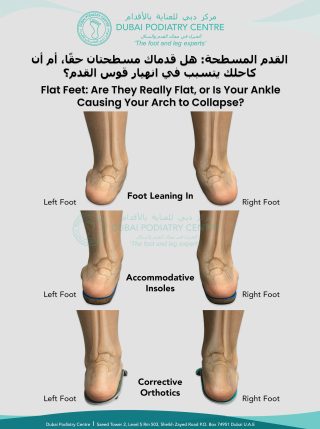
Foot alignment comparison showing inward leaning feet and examples of accommodative and corrective orthotics8. Corrective Versus Accommodative Orthotics: What Is the Difference?

Corrective Orthotics

Corrective orthotics are designed to influence foot and ankle mechanics.

They are commonly used for selected flexible deformities and may include specific alignment angles and posting.

They often require progressive adjustment and monitoring.

Their aim is to improve functional alignment during wear.

Accommodative Orthotics

Accommodative orthotics are designed to support the existing foot shape.

They are commonly used for rigid or painful deformities and focus on cushioning, pressure distribution and comfort.

They are often used as longer term supportive devices.

Their aim is to reduce pressure without forcing realignment.

Both types can be custom made. Both are valuable. But they are designed for different clinical purposes.

The term custom made orthotics alone does not tell you whether a device is corrective or accommodative.

It is important to understand what the orthotic has been designed to achieve.

9. Do All Flat Feet Need Orthotics?

Absolutely not.

A naturally low arch that is comfortable, stable and functioning normally may need no treatment at all.

Likewise, many children have flexible flat feet as part of normal development, and most painless flexible flat feet in children do not require orthotic correction.

Orthotic therapy is considered when there is a clinical reason to intervene, such as pain, fatigue, instability, excessive mechanical loading or functional limitations.

The decision should be based on a proper examination rather than the appearance of the arch alone.

10. How Can You Check Your Feet at Home?

There are a few simple observations you can make.

Step 1: Sit down and look at your arches

Can you see an arch along the inside of your foot?

Step 2: Stand up and look again

Does the arch become significantly lower when you place weight on your feet?

Step 3: Rise gently onto your tiptoes while holding a stable support

Does the arch reappear?

Step 4: Look at your heel alignment

Does the heel appear to tilt outwards, with the ankle region leaning inwards?

These observations may help identify a flexible flatfoot pattern, but they cannot provide a diagnosis on their own.

If your flat feet are painful, becoming progressively flatter, noticeably different between the two sides or associated with stiffness, arrange a professional assessment.

Our Advice at Dubai Podiatry Centre

The most important thing to understand is that flat feet are not automatically abnormal.

Some feet simply have generous natural padding. Some have naturally low arches. Others have flexible arches that lower during standing because of excessive pronation.

A smaller number have rigid structural deformities that require a different approach.

At Dubai Podiatry Centre, we assess the structure and function of the foot and ankle before deciding whether treatment is necessary.

Our aim is not to give every patient a higher arch. It is to understand the individual foot, identify any mechanical problems and recommend the most appropriate treatment.

A healthy foot does not have to look highly arched. It needs to function comfortably and effectively.

Dubai Podiatry Centre

Specialist Foot and Ankle Biomechanical Assessment

www.dubaipodiatry.com

This article is for general educational purposes and does not replace an individual podiatric assessment.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024



Are you experiencing heel pain when you first get out of bed, after standing for long periods, or towards the end of a busy working day? You may be suffering from plantar fasciitis, one of the most common causes of heel and arch pain.

The good news is that there are several simple treatments you can do at home to help relieve discomfort and support your recovery.

What Is Plantar Fasciitis?

The plantar fascia is a strong band of connective tissue that runs underneath your foot, connecting the heel bone to the front of the foot. It helps support the arches of your foot and distributes pressure when you stand, walk and run.

When the plantar fascia is repeatedly placed under excessive tensile stress (stretching and pulling forces), it can become irritated and painful.

This may cause:

  • Pain underneath the heel, particularly with your first steps in the morning
  • Discomfort along the arch or middle of the foot
  • Pain after prolonged standing or walking
  • Occasionally, discomfort extending towards the inner side of the ankle

Although commonly called plantar fasciitis, persistent cases may involve degenerative changes in the fascia rather than inflammation alone.

Why Does Plantar Fasciitis Develop?

At Dubai Podiatry Centre, we pay particular attention to the structural alignment of the feet and ankles.

Three important factors can contribute to increased stress on the plantar fascia:

1. Excessive pronation (hyperpronation)

When the foot rolls excessively inwards during standing or walking, it may increase the tensile load on the plantar fascia.

2. Collapse of the medial longitudinal arch

When the arch along the inside of the foot lowers excessively under weight-bearing pressure, the plantar fascia may be placed under additional strain.

3. Reduced support through the transverse forefoot arch

Changes in forefoot loading and transverse arch support can alter how pressure is distributed through the foot and may contribute to mechanical stress.

Not every patient with plantar fasciitis has these structural problems. Some patients develop symptoms simply because they have been standing for unusually long periods.

Can Plantar Fasciitis Go Away by Itself?

Yes. Some episodes of plantar heel pain are associated with a temporary increase in activity or prolonged standing.

For example:

  • Soldiers on parade: Standing for extended periods without much movement
  • Hairdressers: Working exceptionally long days during busy seasons
  • Chefs: Standing for 12–16 hours during festive periods or special events
  • Retail and hospitality workers: Spending much longer on their feet than usual.

When symptoms are caused by a temporary increase in physical load, they may improve within a few weeks once normal activity levels resume.

However, plantar fasciitis can also last several months. If symptoms persist beyond four weeks, or are getting worse, a podiatric assessment is advisable.

Where structural misalignment is contributing to ongoing strain, corrective orthotics may be recommended to support the arches and improve foot and ankle mechanics. Many patients improve over approximately 12–14 weeks with an appropriate treatment programme, although recovery times vary.

Six Home Treatments for Plantar Fasciitis

1. Warm and Cool Contrast Foot Baths

Contrast foot baths can be a soothing treatment after a long day of standing.

How to do it:

1. Prepare one basin with warm water at approximately 42°C and another with cool water at approximately 22°C
2. Place your feet in the warm water for one minute
3. Transfer them to the cool water for one minute
4. Repeat this cycle five times

Total treatment time: 10 minutes.

Alternating warm and cool temperatures produces changes in superficial circulation and may provide temporary comfort. However, there is limited evidence that contrast baths accelerate plantar fascia healing or remove inflammatory waste products.

Important: Avoid contrast baths if you have diabetes-related loss of sensation, poor circulation, neuropathy or difficulty sensing water temperature. Always check that the water is comfortable and not excessively hot.


Dubai Podiatry Centre blog image about plantar fasciitis and home care for heel pain, showing feet and five cork massage balls2. Massage Your Feet With Cork Roller Balls
Cork massage balls are a simple way to massage the underside of the foot and relieve muscle tension.

Small cork ball: Use gentle circular movements around the fleshy heel pad, avoiding excessive pressure directly over a painful point.

Medium cork ball: Roll slowly underneath the medial arch to massage the soft tissues.

Large cork ball: Use broader rolling movements along the arch and underside of the foot.

Spend approximately 1–2 minutes on each area, using gentle pressure.

Massage should feel comfortable, not painful. Avoid aggressive rolling if your heel is particularly sensitive.


3. Strengthen Your Feet With Towel-Scrunching Exercises

The small intrinsic muscles underneath your feet contribute to foot stability and arch support.

How to do it:

1. Sit comfortably in a chair with your feet flat on the floor
2. Place a small towel in front of your foot
3. Use your toes to scrunch the towel towards you
4. Continue until you have gathered the towel underneath your foot
5. Repeat 5–10 times on each foot, as comfortable

This exercise helps activate the small muscles that support the foot. Start gently and stop if it increases your heel pain.

4. Roll Your Foot Over a Chilled Water Bottle

After a long day of standing, a chilled water bottle can provide welcome relief.

How to do it:

1. Place a 300 ml plastic water bottle in the refrigerator
2. Sit comfortably in a chair
3. Place the bottle underneath your arch
4. Slowly roll your foot backwards and forwards from the arch towards the heel
5. Continue gently for approximately 3 to 5 minutes

A bottle from the refrigerator is preferable to a frozen bottle because it provides gentler cooling without exposing the skin to extreme cold.

The cooling and gentle massage may temporarily reduce pain after prolonged standing.

5. Support Your Foot With Plantar Fascia Tape

Supportive taping can help reduce strain on the plantar fascia during daily activities.

Footerella plantar fascia support tape is designed as a convenient, single-piece application that can be worn during the day.

When applied correctly, supportive taping may help maintain a more comfortable foot position and reduce excessive mechanical loading.

Apply the tape to clean, dry skin in the morning, following the product instructions. Remove it if you experience itching, redness, irritation, numbness or discomfort.

Taping provides temporary support but does not replace corrective orthotics when a significant biomechanical problem requires longer-term management.

6. Choose the Right Socks and Shoes

Footwear can make a significant difference to plantar heel pain.

Soft, cushioned socks

Thick, fluffy, diabetic-style cushioned socks can provide additional comfort and reduce pressure beneath the heel. Choose socks without restrictive seams or tight elastic.

Soft, cushioned shoes

Shoes with adequate heel cushioning may help reduce discomfort, particularly when standing on hard floors.

However, there is an important distinction between cushioning and structural support.

If your feet are neutrally aligned, a comfortable cushioned shoe may provide sufficient relief.

If you have significant hyperpronation or arch instability, a very soft, flexible shoe may not provide enough support and could allow excessive movement.

In these cases, a more supportive shoe combined with appropriately prescribed corrective orthotics may be beneficial.

When Are Corrective Orthotics Needed?

If plantar fasciitis persists, it is important to identify whether the pain is being maintained by abnormal foot mechanics.

At Dubai Podiatry Centre, we assess:

  • Foot and ankle alignment
  • Medial longitudinal arch function
  • Transverse forefoot loading
  • Excessive pronation and other biomechanical abnormalities
  • Walking patterns and pressure distribution

Where clinically indicated, custom corrective orthotics can be designed to support the medial arch, redistribute forefoot pressure and improve the alignment of the foot and ankle.

The aim is to reduce excessive tensile stress on the plantar fascia so that the irritated tissues have an opportunity to recover.

Orthotics are not necessary for every patient, and treatment may also include targeted stretching, strengthening exercises, footwear modification and activity management.

How Long Does Recovery Take?

Recovery depends on the underlying cause, how long symptoms have been present, and whether excessive mechanical loading continues.

A mild episode associated with unusual standing may improve within several weeks.

For persistent plantar fasciitis, improvement may occur over 12–14 weeks with appropriate treatment, although some patients need considerably longer.

The key is not simply to relieve the pain temporarily, but to address the factors placing repeated stress on the plantar fascia.

Our Advice at Dubai Podiatry Centre

If you are suffering from plantar fasciitis, start with simple home treatments: gentle massage, chilled bottle rolling, foot-strengthening exercises, comfortable footwear and appropriate support.

If your pain persists, returns repeatedly, or interferes with normal walking, arrange a podiatric assessment to identify the underlying cause.

Seek medical attention sooner if you have severe pain, significant swelling, redness, fever, numbness, an injury, or difficulty bearing weight.

Dubai Podiatry Centre

Helping patients understand their foot structure, improve their alignment and walk comfortably.

Website: www.dubaipodiatry.com

This article provides general educational information and does not replace an individual clinical assessment.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


Do your feet lean inward or outward when you stand or walk? Excessive inward rolling, known as overpronation, or outward rolling, known as supination, can affect foot alignment and pressure distribution. If you experience foot pain, heel pain or arch discomfort, a biomechanical assessment can help identify your individual support needs.

Watch our video to explore foot alignment and learn how custom-made corrective orthotics can support more comfortable standing and walking.


Custom Foot Orthotics at Dubai Podiatry Centre

At Dubai Podiatry Centre, we assess your foot mechanics and lower-limb alignment to prescribe custom orthotic insoles tailored to your feet. These individually prescribed devices are designed to support the arches, redistribute pressure and help control excessive foot movement.

For patients with symptomatic flat feet, overpronation or supination, custom foot orthotics may help reduce mechanical strain and improve comfort during everyday activities. Your podiatrist will assess whether orthotics are suitable for your symptoms and footwear.

Our Assessment and Orthotic Fitting Process

  • Registration and Consent
  • Consultation
  • Clinical Examination
  • Biomechanical Assessment
  • 3D Body Scanning
  • Photography
  • Gypsum Casting
  • Orthotic Manufacture
  • Fitting
  • Footwear Assessment
  • Final checks and adjustments

From the initial consultation to final fitting, each stage helps us tailor your corrective orthotics to your clinical needs. Footwear assessment and adjustments help ensure the insoles fit appropriately within suitable shoes.

Book a Biomechanical Assessment in Dubai

Looking for a podiatrist in Dubai for flat feet, inward or outward foot leaning, heel pain or arch discomfort? Contact Dubai Podiatry Centre to book a biomechanical assessment and discuss custom-made orthotics, arch support and footwear advice for more comfortable walking.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


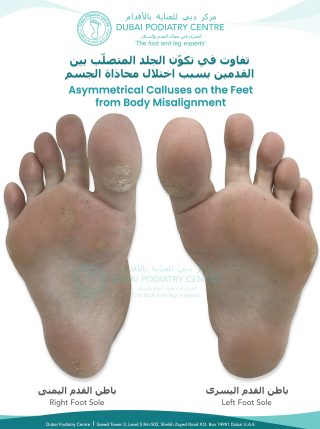
Hard skin under one big toe is more than the other and it’s splitting like paper cuts.

When hard skin keeps coming back, look at why the skin is protecting itself

A common complaint we hear from patients is:

“I constantly get hard skin underneath my big toe. It splits and feels like little paper cuts. I use foot cream, file it and have the callus removed during pedicures, but it always comes back.”


When callus repeatedly develops in exactly the same place, simply removing the hard skin may not address the reason it is forming.

Callus is often the skin’s response to repeated pressure, shear and friction. The location and pattern of the callus can therefore provide useful clues about how forces are travelling through the foot.

A patient with painful, splitting callus

In this particular case, the patient had recurring hard skin underneath her big toe which frequently split, producing a painful sensation similar to paper cuts.

She had tried creams, regular filing and intensive callus removal at pedicure salons, but the problem continued to return.

She also had areas of callus beneath the ball of the foot, particularly underneath the second metatarsal head, as well as callus and a corn around the fifth metatarsal head.

She had also noticed that her feet seemed to be becoming broader.

What was particularly interesting was the difference between her two feet.

The left foot had only a relatively mild amount of hard skin underneath the big toe and forefoot.

The right foot showed considerably more.

Right and left foot soles showing uneven calluses and hard skin beneath the big toes, more pronounced on the right foot

Why was one foot worse than the other?

When we see a significant difference between the right and left feet, we don’t just examine the skin.

We look higher up the body.

In this patient’s assessment, we identified a leg-length discrepancy associated with pelvic asymmetry. Her right side demonstrated a pelvic tilt and altered lower-limb position, with the right foot abducting as she walked.

Instead of progressing straight over the big toe, she was repeatedly rolling across the side of it.

This created increased pressure and shear around the plantar and side of the big toe and first metatarsal region.

The skin was therefore repeatedly being subjected to mechanical stress in the same location.

Removing the callus could make the skin temporarily smoother, but it did not remove the forces that were causing it to develop.

The callus in the middle of the foot told us something different

Not every area of callus on this patient’s foot had the same mechanical explanation.

She also had callus underneath the second metatarsal head and around the fifth metatarsal head.

During her examination, this corresponded with changes in the shape and loading of her forefoot and a reduction in the normal transverse arch across the front of the foot.

As the forefoot spreads and its loading pattern changes, individual metatarsal heads can become more prominent beneath the foot.

The second metatarsal head is a particularly common area of increased plantar pressure.

Between the metatarsal bones and the ground lies an important layer of specialised fibrofatty tissue that helps cushion the foot.

When excessive pressure and shear repeatedly occur over a prominent metatarsal head, the skin may respond by producing additional keratin.

This is what we recognise as callus.

A more concentrated area of pressure can produce a corn.

Callus isn’t necessarily the problem. It can be a clue.

This is an important distinction.

Callus is not simply “dead skin that needs to be removed”

Its distribution can act almost like a map of pressure across the foot.


A podiatrist will therefore look at questions such as:

  • Is the callus symmetrical between the two feet?
  • Is it underneath a particular metatarsal head?
  • Is it underneath or along one side of the big toe?
  • Is there a corn in the centre of the callus?
  • Has the forefoot become broader?
  • Is one arch lower than the other?
  • Does one foot pronate more than the other?
  • Is one leg functionally or structurally longer?
  • Is there pelvic asymmetry?
  • Is the patient’s walking pattern creating excessive pressure or shear?


The position of the callus can help us understand what may be happening mechanically above it.

Why do some calluses crack and feel like paper cuts?

When callus becomes thick, it is less flexible than normal skin.

Every time the toe bends, twists or pushes against the ground, that thickened skin is subjected to movement and shear.

Eventually tiny fissures can develop.

These cracks can feel surprisingly painful, sometimes exactly like a paper cut.

Applying moisturiser may improve the flexibility and condition of the skin, and careful reduction of excessive callus can provide considerable relief.

However, if abnormal pressure and shear remain, the skin may continue to rebuild the callus.

That is why some patients find themselves in a cycle:

Callus forms → callus is filed or removed → skin feels better → the same mechanical forces continue → callus returns


What about people with diabetes or neuropathy?

This is particularly important in patients who have reduced sensation in their feet.

A person with neuropathy may not feel excessive pressure, rubbing, a blister or a developing wound normally.

Callus can itself be an important warning sign of repetitive high pressure, and in a neuropathic foot, areas beneath callus may be at increased risk of tissue breakdown and ulceration.

For this reason, recurrent callus in a person with diabetes, neuropathy or reduced circulation should not simply be aggressively filed or treated with corn-removing acids without appropriate professional assessment.


Why we examine the whole body

At Dubai Podiatry Centre, when we see a recurrent pattern of callus, particularly when one foot is significantly worse than the other, we don’t only look at the piece of hard skin.

We assess the biomechanics producing the pressure.

This can include examining:

Pelvis → hips → knees → ankles → subtalar joints → arches → forefoot → toes

Human bodies are naturally asymmetrical. Small differences are extremely common and do not necessarily cause problems.

It is when that asymmetry produces excessive or repetitive loading that symptoms can begin to appear.

In this patient’s case, the difference between the right and left callus patterns was an important clue.


Why the right and left orthotics may be different

If biomechanical assessment indicates that orthotic therapy is appropriate, the objective is not simply to put identical arch supports underneath both feet.

The two sides of the body may require different corrections.

For example, one orthotic may require a different thickness, inclination or degree of support from the other. The medial arch support may differ, and the forefoot or transverse arch may require different accommodation or correction.

The prescription is based on the individual patient’s examination.

The aim is to redistribute plantar pressure and improve lower-limb and foot mechanics so that the skin is no longer repeatedly exposed to the same excessive forces.


How long does it take for the callus to stop returning?

Skin does not necessarily change immediately when biomechanics are altered.

Even after the source of excessive pressure has been reduced, the skin may continue producing protective keratin for some time.

In clinical practice, we may see the callus pattern gradually reduce over the following months as pressure and shear are better controlled. For some patients, noticeable changes may occur over approximately four to six months, although this varies considerably according to the individual, their footwear, activity, skin condition and underlying biomechanics.

The important point is that we are not simply asking:

“How do we remove this hard skin?”

We are asking:

“Why does this particular piece of skin keep needing to protect itself?”

Once we understand that, we can work on the underlying mechanical cause as well as treating the skin itself.

The takeaway

Recurring callus can be more than a cosmetic problem.

Its location, shape and whether it is symmetrical between the two feet can provide valuable information about pressure, friction, foot structure and walking mechanics.

If the same callus keeps returning despite creams, filing and pedicures, it may be time to stop treating only the surface and investigate what is happening underneath it.

Dubai Podiatry Centre
Looking beyond the callus to understand why it formed.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


A big toenail that becomes white, lifted or separated along one side is often assumed to have a fungal infection. However, not every separated toenail is fungal.

In some patients, the underlying problem is mechanical and begins much further up the foot, at the alignment of the subtalar joint and ankle.

What causes the nail to separate?

When the foot pronates excessively, the subtalar joint and ankle lean inwards and the hallux, or big toe, can begin to internally rotate.

At the same time, the soft tissues and fibrofatty padding beneath the hallux are displaced laterally, towards the second toe.

Instead of remaining directly underneath the big toe, these tissues repeatedly move and press against the structures beneath and around the nail plate during standing and walking.

With thousands of steps each day, this repetitive movement can create an up-and-down and side-to-side mechanical force beneath the nail.

Over time, the nail plate can gradually be pulled away from the nail bed underneath. This produces a characteristic curved or U-shaped area of separation, particularly along the lateral border of the hallux nail.

This type of nail separation is known as onycholysis, but importantly, onycholysis describes the separation itself. It does not tell us what caused it.


An interesting left-versus-right comparison

This photographic example of the toes and feet provides an excellent example because the severity of the nail changes is different between the two feet.

On the left foot, the ankle/subtalar joint pronates approximately 30 degrees, and the lateral separation of the hallux nail plate is considerably greater.

On the right foot, the subtalar joint pronates approximately 12 degrees, and the lateral nail separation is noticeably less extensive.

The asymmetry is clinically interesting because the foot demonstrating the greater degree of pronation also demonstrates the greater degree of nail separation.

Rather than examining the toenail in isolation, we therefore need to examine what is happening to the whole foot, ankle and hallux during weight-bearing and walking.


Why can this be mistaken for fungal nail disease?

When air gets underneath a separated nail plate, the nail can appear white, yellowish or opaque. Debris may also accumulate beneath the separated portion.

Visually, this can resemble a fungal toenail.

However, treating a mechanically separated nail with antifungal treatment alone does not correct the forces repeatedly acting upon the nail.

Where fungal infection is suspected, appropriate clinical assessment and, when indicated, laboratory testing can help distinguish fungal nail disease from other causes of nail dystrophy and onycholysis.


The relationship with ankle alignment

In our clinical observations at Dubai Podiatry Centre, we frequently begin to see secondary foot and nail changes as subtalar joint pronation increases.

When inward deviation becomes more pronounced, mechanical stress upon the hallux can increase. With greater degrees of pronation, we may see progressively wider and deeper lateral nail separation together with increasing rotation or displacement of the hallux.

At very significant degrees of pronation, other structural changes, including hallux valgus, may also coexist.

These degree measurements should not be interpreted as universal diagnostic thresholds. Every patient is assessed individually because foot structure, joint mobility, footwear, activity, gait and other medical or dermatological factors can also influence the appearance of the toenail.

Treatment must address the cause, not simply the nail

If the separation is predominantly mechanical, our objective is to reduce the abnormal forces acting upon the hallux long enough for a healthier nail to grow forward while remaining attached to the nail bed.


Depending upon the individual assessment, treatment may include:

  • Corrective orthotics designed to improve subtalar joint alignment and reduce excessive pronation
  • Toe socks to encourage the toes to remain separated and in a more neutral position
  • Silicone toe liners or separators between the toes where appropriate to assist alignment
  • Footwear with an accommodating toe box, including suitable barefoot-style footwear where clinically appropriate, so that the toes are not compressed or displaced by the shoe

The important principle is consistency.

If a corrective device is worn for only one hour each day but the foot spends the remaining weight-bearing hours returning to its previous position, the mechanical forces responsible for the problem continue.

The objective is to maintain improved foot and toe alignment for as much of the patient’s weight-bearing day as reasonably possible.


How long does the nail take to recover?

Toenails grow slowly.

The recovery period therefore depends partly upon how far backwards the existing separation extends. The damaged portion cannot simply be pushed back onto the nail bed. Instead, we need to reduce the causative mechanical stress and allow healthier nail to gradually grow forward.

For some patients, visible improvement may occur over several months. A mechanically separated area may require approximately four to six months or longer to grow forward sufficiently, depending upon the depth of separation, individual nail-growth rate and how effectively the underlying mechanical problem is controlled.

Look beyond the toenail

A separated toenail does not always mean a fungal toenail.

Sometimes the toenail is simply showing us the end result of a biomechanical problem occurring elsewhere in the foot.

By examining the nail together with the hallux position, plantar soft tissues, subtalar joint, ankle alignment, gait and footwear, we can investigate why the nail is separating rather than treating its appearance alone.

Michelle Duffy Champlin
B.Sc. (Podiatry), M.Ch.S., S.R.Ch. (UK)
Chief Podiatrist
Dubai Podiatry Centre


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


When we think about the arches of our feet, most people immediately picture the large arch running along the inside of the foot.

But there is another, much smaller arch at the front of the foot that we pay very close attention to during a biomechanical assessment at Dubai Podiatry Centre.

It is called the transverse arch.


What is the transverse arch?

The front part of your foot is called the forefoot. It includes the toes and the metatarsal bones, which are the long bones immediately behind your toes.

Across the forefoot, just behind the toes where they connect with the foot, is the transverse arch.

Rather than running from the heel towards the toes like the more familiar medial arch, the transverse arch runs across the foot from side to side.

It is a relatively small arch, but biomechanically it can be extremely important.


What happens when the transverse arch starts to drop?

Over time, the forefoot can begin to spread and the transverse arch can become lowered.

We sometimes describe this to patients as the metatarsal bones beginning to “avalanche” forwards and downwards.

Although this change is occurring in a relatively small area at the front of the foot, it can influence the way the rest of the foot functions.

The metatarsal bones do not work independently from the remainder of the foot. They form part of the interconnected structure of the foot and contribute to its stability and function during standing and walking.

As the forefoot begins to change position, we may also see changes occurring through the larger medial arch, the midfoot and eventually the mechanics around the ankle.

This is why we never look at the transverse arch in isolation.


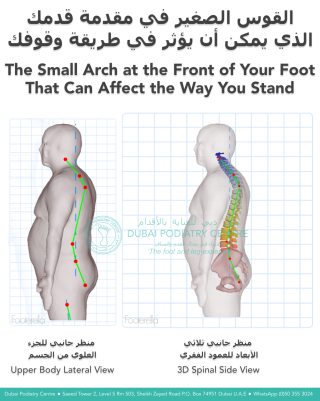
3D postural assessment showing how a collapsed forefoot transverse arch may affect standing posture and spinal alignment


Are you beginning to look hunched forwards?

One of the observations that can prompt us to investigate the forefoot is a change in a person’s stature.

Sometimes a patient, or their family, will say that they are beginning to “look hunchbacked” or that they appear to be leaning forwards.

The head may be sitting further forwards, the shoulders may appear more rounded and the person can develop an increasingly stooped appearance.

There are, of course, many different reasons why somebody may develop a forward head position or stooped posture. It should never automatically be assumed that it is coming from the feet.

However, it is one of the physical signs that makes us look more carefully at the person’s overall biomechanics.

We look at the person from the side and assess their stature. We look at the position of the head and shoulders. We observe how they stand and walk.

Then we investigate what is happening underneath them.

In particular, we examine the sole of the foot and the forefoot to see what has happened to the transverse arch.

If that small arch has dropped and the metatarsal bones have moved forwards and downwards, it may be contributing to a chain of biomechanical changes occurring further up the body.

Your feet form the foundation of your posture


The feet provide the foundation for the body when we stand and walk.

Changes in that foundation can sometimes contribute to compensations further up the biomechanical chain.

This is why a person’s posture can give us clues about what we should investigate in their feet.

A forward head, rounded shoulders, a stooped stance or a tendency to shuffle when walking does not diagnose a foot problem. However, these observations can be a reason to include the feet in the assessment rather than concentrating only on the upper body.

Sometimes the clue is visible at the shoulders and head, while part of the biomechanical problem may be much further down, at the sole of the foot.


Why we look for problems early

One of the reasons we pay such close attention to the transverse arch is that it can give us an opportunity to identify biomechanical changes relatively early.

If the transverse arch has started to lower but the remainder of the foot is still relatively well controlled, treatment can be much simpler.

Where appropriate, a custom corrective orthotic can be designed to support and lift the transverse arch and improve the mechanical stability of the forefoot.

The objective is not simply to put something soft underneath a painful area. It is to address the position and function of the forefoot as part of the mechanics of the entire foot.


What if the whole foot has already started to collapse?

More advanced biomechanical changes can also be managed. It simply requires a different approach.

If changes have progressed through the forefoot, midfoot and ankle, attempting to correct everything at once may not be appropriate or comfortable.

Instead, orthotic therapy may need to be carried out step by step and stage by stage.

We may initially need to address the forefoot and transverse arch. As the foot adapts, we can reassess the midfoot, medial arch, rearfoot, heel and ankle mechanics.

This process naturally takes longer than treating an early biomechanical change.

A small arch can give us a big clue

The transverse arch is a relatively small structure, but it can tell us a great deal about what is happening throughout the foot.

This is why we don’t assess feet simply by asking, “Where does it hurt?”

We look at the toes, forefoot, midfoot, heel and ankle. We look at how you stand. We look at the position of your shoulders and head. We watch how you walk.

If somebody tells you that you are beginning to look more hunched over, or you notice that your head is increasingly sitting forwards and your shoulders are becoming rounded, there can be many possible explanations.

But don’t forget to look down.

A biomechanical assessment of the feet, and particularly that small transverse arch underneath the forefoot, may provide another important piece of the puzzle.

The earlier we identify a change in foot biomechanics, the easier it may be to manage before it progresses further.


Dubai Podiatry Centre
Biomechanical Foot Assessment and Custom Orthotic Therapy


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


Flat feet in children are common, but parents may become concerned when a child’s feet or ankles roll inward while standing or walking. This inward movement is known as overpronation and may affect foot posture, ankle stability, balance and walking comfort.

At Dubai Podiatry Centre, our podiatrists assess children’s flat feet and walking patterns to determine whether additional support, such as custom-made orthotics, may be beneficial.


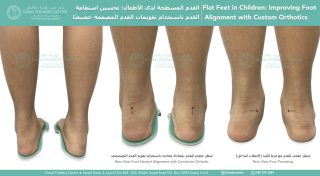
Child’s flat feet showing overpronation and improved neutral foot alignment with custom orthotics in Dubai

What Are Flat Feet in Children?

Flat feet occur when the arches of the feet appear lowered or make increased contact with the ground. In some children, the heels and ankles may also lean inward, causing the feet to overpronate.

Although flat feet do not always cause problems, a podiatry assessment may be recommended if your child experiences:

  • Foot, heel, ankle or knee pain
  • Tired or aching legs
  • Frequent tripping or poor balance
  • Difficulty walking or participating in sports
  • Uneven or excessive shoe wear
  • Ankles that visibly roll inward
  • Changes in posture or walking pattern

Recognising these signs early allows the child’s foot posture, movement and support requirements to be professionally evaluated.

How Overpronation Can Affect Foot Alignment

When a child’s feet overpronate, the heels and ankles lean inward instead of remaining in a more neutral position. This may change how pressure is distributed across the feet and influence the alignment of the lower limbs.

The comparison image demonstrates the rear view of pronating feet and the improved neutral alignment achieved while standing on corrective orthotics. The orthotics provide support beneath the feet and help stabilise the heels and ankles.

Custom Orthotics for Children’s Flat Feet

Custom orthotics are individually made to match the shape, posture and biomechanical needs of each child’s feet. Unlike standard insoles, they are created following a professional foot and walking assessment.

Corrective orthotics may help to:

  • Support the arches of the feet
  • Reduce excessive inward rolling
  • Stabilise the heels and ankles
  • Improve foot and lower-limb alignment
  • Distribute pressure more evenly
  • Support balance and walking comfort
  • Reduce strain on the feet and legs

Every child’s feet are different, which is why orthotics should be designed according to their individual assessment rather than selected as a one-size-fits-all solution.

Children’s Biomechanical Foot Assessment in Dubai

At Dubai Podiatry Centre, a children’s biomechanical assessment examines foot posture, ankle alignment, lower-limb movement and walking pattern. The podiatrist will determine whether custom orthotics are appropriate and explain the recommended treatment plan.

Regular reviews may also be advised to monitor the child’s progress, comfort and changing needs as they grow.

Book a Children’s Flat Feet Assessment in Dubai

If your child’s feet roll inward or you have concerns about flat feet, foot pain, balance or walking, professional assessment can help identify their individual support requirements.

Book a children’s flat feet and overpronation assessment with Dubai Podiatry Centre on Sheikh Zayed Road. Our podiatrists provide personalised foot assessments and custom orthotics for children in Dubai.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


Flat feet can affect more than just the feet. When the arches collapse excessively during standing or walking, the feet may roll inwards—a movement known as overpronation. This can alter the position of the heels and affect the alignment of the ankles, knees and hips.

Over time, poor foot alignment may place additional strain on the muscles, tendons and joints throughout the lower limbs.


Signs and Symptoms of Flat Feet

Not everyone with flat feet requires treatment. However, adults and children whose flat feet cause pain or affect their mobility may experience:

  • Tired or aching feet
  • Heel, arch or ankle pain
  • Knee or hip discomfort
  • Reduced walking endurance
  • Difficulty standing for long periods
  • Uneven shoe wear
  • Changes in walking pattern

A professional foot and gait assessment can help determine whether flat feet or overpronation are contributing to these symptoms.

Corrective Orthotics for Flat Feet

Not all insoles provide the same type of support. Cushioned insoles are primarily designed to improve comfort and redistribute pressure. Corrective orthotics are designed to control excessive foot movement, support the position of the heels and improve lower-limb alignment.

When clinically appropriate, custom-made corrective orthotics may help reduce excessive strain on the feet and legs, improve stability and make standing, walking and daily activities more comfortable.

Children’s and adults’ feet have different requirements. For this reason, corrective orthotics should be individually prescribed following a detailed assessment rather than selected as a one-size-fits-all solution.

Biomechanical Assessment at Dubai Podiatry Centre

At Dubai Podiatry Centre, flat feet treatment begins with a comprehensive biomechanical assessment. Our podiatrist evaluates:

  • Foot posture and arch position
  • Heel and ankle alignment
  • Walking pattern and gait
  • Muscle function
  • Joint movement
  • Lower-limb biomechanics

The assessment helps identify how the feet are functioning and whether custom-made corrective orthotics are suitable for you or your child.

Book a biomechanical assessment at Dubai Podiatry Centre to learn more about flat feet, overpronation and corrective orthotic treatment.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


Choosing the right shoes is especially important for children who wear custom foot orthotics. Orthotic-friendly shoes should provide enough space for the devices while keeping the feet secure, comfortable and properly supported throughout the day.

At Dubai Podiatry Centre, we help parents choose suitable children’s footwear for custom orthotics, flat feet, overpronation and other foot conditions.

Why Are Orthotic-Friendly Shoes Important?

Custom orthotics are designed to support a child’s feet, improve foot function and distribute pressure more evenly. However, the orthotics must fit correctly inside the shoes to work as intended.

Shoes that are too narrow, shallow, soft or unstable may cause the orthotics to move, lift the heel or create pressure and discomfort. The best shoes for kids wearing orthotics should securely accommodate the devices without restricting the feet.

What to Look for in Children’s Shoes for Orthotics

When shopping for supportive kids’ shoes, look for the following features:

Removable Insoles

Shoes with removable insoles create additional space for custom orthotics. The original insoles should normally be removed before inserting the orthotic devices.

A Wide Toe Box

A wide, rounded toe box allows the toes to move naturally without rubbing or being compressed. This is particularly important as children’s feet continue to grow.

Adequate Width and Depth

The shoes must be deep and wide enough to accommodate the orthotics without making the fit too tight or pushing the feet upwards.

A Firm Heel Counter

A supportive heel counter helps hold the heel securely and reduces unwanted movement inside the shoe. This can provide additional stability for children with flat feet or overpronation.

Adjustable Fastenings

Laces, straps or adjustable closures help keep the feet and orthotics securely positioned. They also allow the fit to be adjusted as needed.

A Supportive Sole

Choose shoes with a stable sole that bends naturally near the toes rather than twisting or folding easily through the middle.

Lightweight and Durable Materials

Children need footwear that is comfortable for daily movement while being strong enough for school, sports and everyday activities.

Shoes for Children With Flat Feet and Overpronation

Children with flat feet or overpronation may require extra support to improve stability and reduce excessive inward rolling of the feet. Combining professionally prescribed custom orthotics with appropriately fitted supportive shoes can improve walking comfort and help the orthotics work effectively.

Every child’s feet are different. The best shoe is not simply the most expensive or popular option—it is the shoe that fits the child’s feet and orthotics correctly.

Tips for Finding the Correct Fit

Always take your child’s orthotics when shopping for new shoes. Insert the devices and ask your child to walk in the shoes before making a decision.

Check that:

  • The orthotics sit flat and securely inside the shoes.
  • The heels do not slip while walking.
  • The toes have enough room to move comfortably.
  • There are no areas of rubbing or pressure.
  • The shoes feel secure without being tight.
  • Your child can walk naturally and comfortably.

Do not automatically buy a larger shoe size to create space for the orthotics. A shoe that is too large may allow the feet and orthotics to move excessively. Instead, choose footwear with the correct width, depth and internal shape.

Expert Footwear Advice in Dubai

If your child has flat feet, overpronation, foot discomfort or difficulty finding shoes that fit their orthotics, a professional foot assessment can help.

Watch our video to discover the best supportive shoes for kids wearing orthotics, recommended by Michelle Duffy Champlin, a podiatrist at Dubai Podiatry Centre.

Contact Dubai Podiatry Centre to arrange a children’s foot assessment and receive professional advice about custom orthotics and supportive footwear in Dubai.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


A patient recently attended Dubai Podiatry Centre with an interesting story that led to a much wider discussion about menopause, movement, muscle strength and the importance of keeping our bodies active as we age.

She had completed menopause and described how, during the previous year, she had gained weight and noticed a significant change in her muscle tone and the way her body felt. She felt that she had lost some of the strength, firmness and resilience that she previously had.

More recently, however, she had become very proactive about her health. Under professional guidance, she had been exploring treatments aimed at supporting her health after menopause, while also paying closer attention to her vitamin D and calcium intake. Most importantly from our perspective, she had started walking every morning and was feeling considerably better.

She also mentioned feeling particularly motivated after listening to Mel Robbins’ podcast discussions about longevity and maintaining strength and health as we get older.

This prompted a fascinating conversation in the clinic about something we often discuss with our patients:

When it comes to movement, we really do have to use it or lose it.

Think of Your Fascia Like a Springy Spider’s Web

Fascia is the connective tissue network that runs throughout the body, surrounding and connecting muscles, bones and other structures.

I often describe it to patients as being a little like a three-dimensional spider’s web running throughout the body.

When we are young and active, our bodies tend to have a wonderful natural springiness. We run, skip, jump, change direction, climb stairs and step over obstacles without giving these movements much thought.

As we get older, particularly if our activity levels reduce, we can gradually stop performing many of these movements.

We may still walk, but perhaps we no longer skip.

We may climb stairs, but rarely jump.

We may exercise, but always in straight, predictable movements.

Gradually, we can lose some of our strength, agility, balance and natural rebound.

The answer is not necessarily extreme exercise. It is about continuing to give our bodies a variety of movements.

Walking and Our “Second Heart”

One of the best forms of exercise remains one of the simplest: walking.

The calf muscles are sometimes referred to as our “second heart” because their contractions help pump venous blood from the lower legs back towards the heart.

Every time we walk and activate our calf muscles, we are helping this natural pumping mechanism.

Regular walking is therefore wonderful for maintaining calf muscle activity, circulation, cardiovascular fitness, mobility and general wellbeing.

But walking does not have to be the only movement we practise.

Bring Back a Little Agility

I am delighted to see movements similar to traditional step aerobics becoming popular again.

Step exercises require us to lift our feet, judge the height of a step, transfer our weight, turn, coordinate our legs and maintain our balance.

These are valuable skills.

As we age, maintaining the ability to change direction, step sideways, lift our feet over an obstacle and react to an irregular surface becomes increasingly important.

Simple activities can include:

  • Walking regularly
  • Stepping up and down from a low exercise step
  • Side stepping
  • Gentle direction changes
  • Appropriate strength exercises
  • Balance exercises
  • Practising safely stepping over small obstacles
  • Maintaining the ability to get up and down from the floor

The exercises chosen should, of course, be appropriate for the individual’s health, balance, strength and medical history.

But What Happens When Walking Hurts?

Our patient’s motivation was excellent, but there was another part of the story.

She was experiencing plantar fascia discomfort as well as lower back and shoulder blade pain, particularly on one side.

Her chiropractor had also identified significant asymmetry and felt that her alignment could be contributing to her symptoms when walking.

This is an important point.

We frequently encourage patients to walk more, but if somebody is significantly mechanically misaligned, repeatedly walking with that imbalance can sometimes continue to aggravate certain tissues.

We therefore assessed her using our 3D scanning system.

The scan demonstrated an apparent leg length discrepancy of approximately 3.1 cm, with the left side measuring longer. For somebody approximately 5 feet 4 inches tall, this represented a considerable asymmetry.

Rather than simply treating the painful plantar fascia, we needed to look at what was happening throughout the body.

The Feet Can Affect What Happens Above Them

The feet are the foundation of the body when we stand and walk.

If one side functions differently from the other, compensation can occur through the legs, pelvis and higher into the body.

I sometimes describe this as a Z-shaped compensation pattern.

The body does not necessarily remain neatly vertical when trying to accommodate an imbalance. Soft tissues tighten, joints adapt and the pelvis and upper body may compensate in different directions.

For this patient, we therefore made the left and right orthotics quite differently.

The angles and thicknesses were individually designed to improve her overall alignment rather than simply giving her two identical insoles.

An Immediate Change From 3.1 cm to 1.3 cm

We then repeated her 3D assessment while she was standing on her new orthotics.

The apparent leg length discrepancy reduced immediately from approximately 3.1 cm to 1.3 cm.

That was an excellent initial change.

Importantly, however, our aim was not to make both sides completely equal on the first day.

The body has been compensating for its existing position for a long time. Muscles, fascia and other soft tissues have adapted to that position too.

Changing everything immediately can therefore be too much.

Instead, we make an initial correction and allow the body time to adapt.

Why We Review Again After 6–12 Weeks

We will review this patient again after approximately 6–12 weeks.

During this period, the muscles and soft tissues have time to respond to the altered skeletal alignment.

An apparent leg length discrepancy can sometimes look greater during the initial assessment because the measurement is influenced not only by the bones themselves but also by rotation and compensation occurring throughout the body.

As these compensatory patterns reduce, the apparent discrepancy may also change.

At the review appointment, we can repeat the assessment and adjust the orthotics according to how her body has responded.

This gradual approach allows us to work with the body rather than trying to force an immediate correction.

Healthy Ageing Starts From the Ground Up

One of the most positive things about this patient’s story was her motivation.

She wanted to walk.

She wanted to become stronger.

She wanted to maintain her mobility and enjoy her body as she moved into the next stage of her life.

That is exactly what we want to encourage.

Menopause and ageing can bring changes in muscle mass, bone health and body composition, but becoming older should not mean accepting that we can no longer move freely.

Walk.

Maintain your strength.

Challenge your balance.

Practise changing direction.

Lift your feet.

Use stairs and steps when appropriate.

And, if you used to skip, perhaps don’t completely forget how to skip.

Our bodies are designed for movement.

Use your movement, maintain your strength, and look after the foundations carrying you through life: your feet.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


Copyright Dubai Podiatry 2026. All rights reserved.

WhatsApp us