fbpx

Please wait...


BLOG

No more posts

Not all flat feet are a problem. In fact, many people who believe they have flat feet have perfectly normal, healthy feet that require no treatment whatsoever.

At Dubai Podiatry Centre, one of the most important parts of assessing flat feet is understanding why the arch appears low.

There are several different types of flat feet, and the treatment, if any is required, depends on the structure, flexibility and alignment of the foot and ankle.

1. Some Feet Are Naturally Flat and Perfectly Healthy

Feet come in many different shapes and structures.

Some people naturally have high arches, while others have lower arches. Both can be completely normal.

One particularly interesting difference is the amount of natural fibrofatty padding underneath the foot.

The Importance of Natural Foot Padding

The sole of the foot contains specialised fibrofatty tissue that cushions the bones and helps absorb pressure when we stand and walk.

The amount and distribution of this padding varies between individuals, influenced by genetics, age and other factors.

Some people have generous natural padding underneath their feet, making the arch appear lower than it actually is.

Others have less visible soft tissue padding, making their feet look more bony and highly arched.

A well padded foot may therefore look flat even when the underlying arch structure is perfectly normal.

This is not necessarily related to obesity, and it does not mean the foot requires correction.

In fact, natural plantar cushioning can be particularly beneficial as we get older, when loss or displacement of the protective fat pads may cause discomfort beneath the bones of the feet.

The important message is simple: a foot that looks flat is not necessarily a structurally flat foot.

2. How Do We Know Whether a Foot Is Really Flat?

At Dubai Podiatry Centre, we examine the foot in several positions.

We look at the foot when the patient is sitting, standing and rising onto their tiptoes.

We assess three important factors:

Arch formation: Is there a well formed medial arch when the foot is not bearing weight?

Flexibility: Does the arch reappear when the patient stands on tiptoes, and can the foot be repositioned comfortably?

Ankle alignment: Does the ankle or heel lean inwards when the patient stands?

These observations help distinguish a naturally low arch, a flexible flat foot and a rigid flat foot.
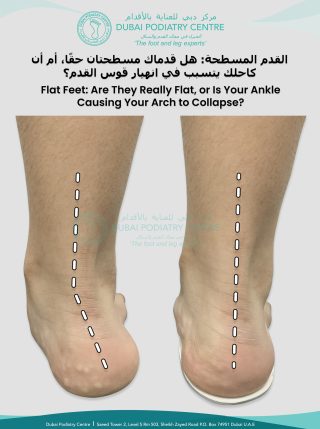
Rear view comparing ankle and heel alignment, illustrating how inward ankle lean can contribute to a lowered foot arch3. The Hyperpronated Foot: When the Ankle Collapses Inwards

One of the common patterns we assess is excessive pronation, also known as hyperpronation.

This is particularly interesting because the patient may have a beautifully formed arch when sitting.

However, when they stand, the arch lowers significantly.

Why Does This Happen?

When the foot bears weight, the heel may tilt outwards and the ankle region may appear to lean inwards.

This movement is often accompanied by lowering of the medial longitudinal arch.

In other words, the arch is present when the foot is unloaded, but it becomes much flatter when the patient stands.

This is a flexible flatfoot pattern associated with excessive pronation.

Pronation is a normal and necessary movement during walking. It becomes clinically relevant when the amount or timing of movement contributes to symptoms, instability or excessive mechanical loading.

Not every hyperpronated foot requires treatment. We consider the patient’s symptoms, age, mobility, function and overall alignment before recommending intervention.

4. What About Ligamentous Laxity?

Some people have naturally more flexible ligaments and joints.

This is known as ligamentous laxity or joint hypermobility.

In these individuals, the arches may lower more easily during standing.

We may also observe increased movement elsewhere in the body, such as hyperextension of the knees, increased flexibility of the ankles, greater movement through the hips and pelvis, and generalised joint hypermobility.

Ligamentous laxity can contribute to flexible flat feet, although it is not present in every patient with low arches.

A full assessment helps us understand whether the flexibility is normal for that individual or is contributing to pain and instability.

5. Flexible Flat Feet Versus Rigid Flat Feet

This is one of the most important distinctions when assessing foot structure.

Flexible Flat Feet

A flexible flat foot typically has an arch when sitting or when the foot is not bearing weight.

When standing, the arch lowers.

When the patient rises onto their tiptoes, the arch may reappear.

The foot can usually be repositioned without significant restriction.

Where excessive pronation is contributing to symptoms or functional problems, corrective orthotic therapy may be considered.

Rigid Flat Feet

A rigid flat foot remains flat even when the foot is not bearing weight.

The arch does not reappear normally when the patient rises onto their tiptoes, and the foot may have restricted movement.

Possible causes include arthritis affecting the joints of the foot, structural changes to the bones or joints, tarsal coalition, long standing deformity and advanced adult acquired flatfoot deformity.

Rigid flat feet require careful assessment. Imaging or specialist referral may be necessary, particularly when pain, progressive deformity or restricted movement is present.

6. Corrective Orthotics: Supporting a Flexible Foot in Better Alignment

At Dubai Podiatry Centre, we distinguish between two important categories of custom made orthotics: corrective and accommodative.

They are not the same, and they serve different purposes.

Corrective orthotics are designed to influence the position and mechanics of a flexible foot and ankle.

For example, a patient may have a well formed arch when sitting, but the arch lowers excessively when standing because of hyperpronation.

When clinically appropriate, a corrective orthotic can be designed using the foot’s non weightbearing shape and its assessed alignment.

The orthotic is then manufactured with specific contours and posting angles intended to improve support and influence how the foot and ankle function during weightbearing.

How Corrective Orthotic Therapy Works

At Dubai Podiatry Centre, our approach includes:

1. Examining the patient’s foot and ankle alignment
2. Assessing the shape of the foot without weightbearing
3. Determining how much of the pronation is flexible and correctable
4. Designing a custom orthotic with the appropriate arch support and alignment features
5. Introducing the orthotic gradually, according to the patient’s tolerance and treatment plan
6. Monitoring comfort, symptoms and foot function over time

The aim is to reduce excessive mechanical loading and improve functional alignment.

Corrective orthotics are individualised and may require adjustments as the patient’s symptoms, footwear, activity or foot mechanics change.

However, wearing corrective orthotics does not necessarily permanently reshape the foot or ankle. Their principal mechanical effect occurs while they are being worn.

7. Accommodative Orthotics: Supporting the Foot Without Forcing Correction

Accommodative orthotics are also custom made, but they have a different purpose.

Rather than attempting to reposition a foot into a new alignment, they are designed to fit and support its existing structure.

These orthotics are particularly useful when the foot cannot comfortably be moved into a neutral position.

Examples include rigid flat feet, arthritic feet with restricted joint movement, structural bone or joint deformities, feet with painful pressure points and certain complex or sensitive foot conditions.

An accommodative orthotic can distribute pressure more evenly, provide cushioning and support the foot in a comfortable position.

It does not attempt to force a rigid or arthritic foot into an alignment that the joints cannot achieve.

These orthotics may be used for many years, although they require periodic assessment and replacement as materials wear or the patient’s needs change.
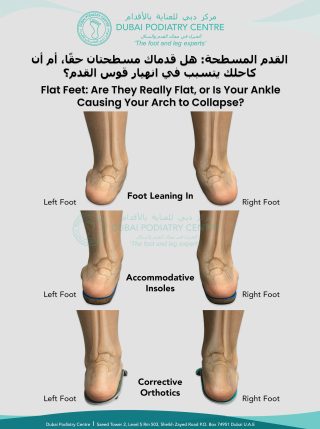
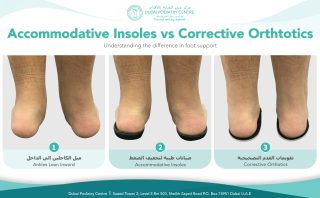
Foot alignment comparison showing inward leaning feet and examples of accommodative and corrective orthotics8. Corrective Versus Accommodative Orthotics: What Is the Difference?

Corrective Orthotics

Corrective orthotics are designed to influence foot and ankle mechanics.

They are commonly used for selected flexible deformities and may include specific alignment angles and posting.

They often require progressive adjustment and monitoring.

Their aim is to improve functional alignment during wear.

Accommodative Orthotics

Accommodative orthotics are designed to support the existing foot shape.

They are commonly used for rigid or painful deformities and focus on cushioning, pressure distribution and comfort.

They are often used as longer term supportive devices.

Their aim is to reduce pressure without forcing realignment.

Both types can be custom made. Both are valuable. But they are designed for different clinical purposes.

The term custom made orthotics alone does not tell you whether a device is corrective or accommodative.

It is important to understand what the orthotic has been designed to achieve.

9. Do All Flat Feet Need Orthotics?

Absolutely not.

A naturally low arch that is comfortable, stable and functioning normally may need no treatment at all.

Likewise, many children have flexible flat feet as part of normal development, and most painless flexible flat feet in children do not require orthotic correction.

Orthotic therapy is considered when there is a clinical reason to intervene, such as pain, fatigue, instability, excessive mechanical loading or functional limitations.

The decision should be based on a proper examination rather than the appearance of the arch alone.

10. How Can You Check Your Feet at Home?

There are a few simple observations you can make.

Step 1: Sit down and look at your arches

Can you see an arch along the inside of your foot?

Step 2: Stand up and look again

Does the arch become significantly lower when you place weight on your feet?

Step 3: Rise gently onto your tiptoes while holding a stable support

Does the arch reappear?

Step 4: Look at your heel alignment

Does the heel appear to tilt outwards, with the ankle region leaning inwards?

These observations may help identify a flexible flatfoot pattern, but they cannot provide a diagnosis on their own.

If your flat feet are painful, becoming progressively flatter, noticeably different between the two sides or associated with stiffness, arrange a professional assessment.

Our Advice at Dubai Podiatry Centre

The most important thing to understand is that flat feet are not automatically abnormal.

Some feet simply have generous natural padding. Some have naturally low arches. Others have flexible arches that lower during standing because of excessive pronation.

A smaller number have rigid structural deformities that require a different approach.

At Dubai Podiatry Centre, we assess the structure and function of the foot and ankle before deciding whether treatment is necessary.

Our aim is not to give every patient a higher arch. It is to understand the individual foot, identify any mechanical problems and recommend the most appropriate treatment.

A healthy foot does not have to look highly arched. It needs to function comfortably and effectively.

Dubai Podiatry Centre

Specialist Foot and Ankle Biomechanical Assessment

www.dubaipodiatry.com

This article is for general educational purposes and does not replace an individual podiatric assessment.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024



Are you experiencing heel pain when you first get out of bed, after standing for long periods, or towards the end of a busy working day? You may be suffering from plantar fasciitis, one of the most common causes of heel and arch pain.

The good news is that there are several simple treatments you can do at home to help relieve discomfort and support your recovery.

What Is Plantar Fasciitis?

The plantar fascia is a strong band of connective tissue that runs underneath your foot, connecting the heel bone to the front of the foot. It helps support the arches of your foot and distributes pressure when you stand, walk and run.

When the plantar fascia is repeatedly placed under excessive tensile stress (stretching and pulling forces), it can become irritated and painful.

This may cause:

  • Pain underneath the heel, particularly with your first steps in the morning
  • Discomfort along the arch or middle of the foot
  • Pain after prolonged standing or walking
  • Occasionally, discomfort extending towards the inner side of the ankle

Although commonly called plantar fasciitis, persistent cases may involve degenerative changes in the fascia rather than inflammation alone.

Why Does Plantar Fasciitis Develop?

At Dubai Podiatry Centre, we pay particular attention to the structural alignment of the feet and ankles.

Three important factors can contribute to increased stress on the plantar fascia:

1. Excessive pronation (hyperpronation)

When the foot rolls excessively inwards during standing or walking, it may increase the tensile load on the plantar fascia.

2. Collapse of the medial longitudinal arch

When the arch along the inside of the foot lowers excessively under weight-bearing pressure, the plantar fascia may be placed under additional strain.

3. Reduced support through the transverse forefoot arch

Changes in forefoot loading and transverse arch support can alter how pressure is distributed through the foot and may contribute to mechanical stress.

Not every patient with plantar fasciitis has these structural problems. Some patients develop symptoms simply because they have been standing for unusually long periods.

Can Plantar Fasciitis Go Away by Itself?

Yes. Some episodes of plantar heel pain are associated with a temporary increase in activity or prolonged standing.

For example:

  • Soldiers on parade: Standing for extended periods without much movement
  • Hairdressers: Working exceptionally long days during busy seasons
  • Chefs: Standing for 12–16 hours during festive periods or special events
  • Retail and hospitality workers: Spending much longer on their feet than usual.

When symptoms are caused by a temporary increase in physical load, they may improve within a few weeks once normal activity levels resume.

However, plantar fasciitis can also last several months. If symptoms persist beyond four weeks, or are getting worse, a podiatric assessment is advisable.

Where structural misalignment is contributing to ongoing strain, corrective orthotics may be recommended to support the arches and improve foot and ankle mechanics. Many patients improve over approximately 12–14 weeks with an appropriate treatment programme, although recovery times vary.

Six Home Treatments for Plantar Fasciitis

1. Warm and Cool Contrast Foot Baths

Contrast foot baths can be a soothing treatment after a long day of standing.

How to do it:

1. Prepare one basin with warm water at approximately 42°C and another with cool water at approximately 22°C
2. Place your feet in the warm water for one minute
3. Transfer them to the cool water for one minute
4. Repeat this cycle five times

Total treatment time: 10 minutes.

Alternating warm and cool temperatures produces changes in superficial circulation and may provide temporary comfort. However, there is limited evidence that contrast baths accelerate plantar fascia healing or remove inflammatory waste products.

Important: Avoid contrast baths if you have diabetes-related loss of sensation, poor circulation, neuropathy or difficulty sensing water temperature. Always check that the water is comfortable and not excessively hot.


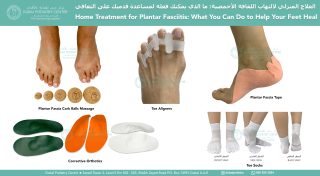
Dubai Podiatry Centre blog image about plantar fasciitis and home care for heel pain, showing feet and five cork massage balls2. Massage Your Feet With Cork Roller Balls
Cork massage balls are a simple way to massage the underside of the foot and relieve muscle tension.

Small cork ball: Use gentle circular movements around the fleshy heel pad, avoiding excessive pressure directly over a painful point.

Medium cork ball: Roll slowly underneath the medial arch to massage the soft tissues.

Large cork ball: Use broader rolling movements along the arch and underside of the foot.

Spend approximately 1–2 minutes on each area, using gentle pressure.

Massage should feel comfortable, not painful. Avoid aggressive rolling if your heel is particularly sensitive.


3. Strengthen Your Feet With Towel-Scrunching Exercises

The small intrinsic muscles underneath your feet contribute to foot stability and arch support.

How to do it:

1. Sit comfortably in a chair with your feet flat on the floor
2. Place a small towel in front of your foot
3. Use your toes to scrunch the towel towards you
4. Continue until you have gathered the towel underneath your foot
5. Repeat 5–10 times on each foot, as comfortable

This exercise helps activate the small muscles that support the foot. Start gently and stop if it increases your heel pain.

4. Roll Your Foot Over a Chilled Water Bottle

After a long day of standing, a chilled water bottle can provide welcome relief.

How to do it:

1. Place a 300 ml plastic water bottle in the refrigerator
2. Sit comfortably in a chair
3. Place the bottle underneath your arch
4. Slowly roll your foot backwards and forwards from the arch towards the heel
5. Continue gently for approximately 3 to 5 minutes

A bottle from the refrigerator is preferable to a frozen bottle because it provides gentler cooling without exposing the skin to extreme cold.

The cooling and gentle massage may temporarily reduce pain after prolonged standing.

5. Support Your Foot With Plantar Fascia Tape

Supportive taping can help reduce strain on the plantar fascia during daily activities.

Footerella plantar fascia support tape is designed as a convenient, single-piece application that can be worn during the day.

When applied correctly, supportive taping may help maintain a more comfortable foot position and reduce excessive mechanical loading.

Apply the tape to clean, dry skin in the morning, following the product instructions. Remove it if you experience itching, redness, irritation, numbness or discomfort.

Taping provides temporary support but does not replace corrective orthotics when a significant biomechanical problem requires longer-term management.

6. Choose the Right Socks and Shoes

Footwear can make a significant difference to plantar heel pain.

Soft, cushioned socks

Thick, fluffy, diabetic-style cushioned socks can provide additional comfort and reduce pressure beneath the heel. Choose socks without restrictive seams or tight elastic.

Soft, cushioned shoes

Shoes with adequate heel cushioning may help reduce discomfort, particularly when standing on hard floors.

However, there is an important distinction between cushioning and structural support.

If your feet are neutrally aligned, a comfortable cushioned shoe may provide sufficient relief.

If you have significant hyperpronation or arch instability, a very soft, flexible shoe may not provide enough support and could allow excessive movement.

In these cases, a more supportive shoe combined with appropriately prescribed corrective orthotics may be beneficial.

When Are Corrective Orthotics Needed?

If plantar fasciitis persists, it is important to identify whether the pain is being maintained by abnormal foot mechanics.

At Dubai Podiatry Centre, we assess:

  • Foot and ankle alignment
  • Medial longitudinal arch function
  • Transverse forefoot loading
  • Excessive pronation and other biomechanical abnormalities
  • Walking patterns and pressure distribution

Where clinically indicated, custom corrective orthotics can be designed to support the medial arch, redistribute forefoot pressure and improve the alignment of the foot and ankle.

The aim is to reduce excessive tensile stress on the plantar fascia so that the irritated tissues have an opportunity to recover.

Orthotics are not necessary for every patient, and treatment may also include targeted stretching, strengthening exercises, footwear modification and activity management.

How Long Does Recovery Take?

Recovery depends on the underlying cause, how long symptoms have been present, and whether excessive mechanical loading continues.

A mild episode associated with unusual standing may improve within several weeks.

For persistent plantar fasciitis, improvement may occur over 12–14 weeks with appropriate treatment, although some patients need considerably longer.

The key is not simply to relieve the pain temporarily, but to address the factors placing repeated stress on the plantar fascia.

Our Advice at Dubai Podiatry Centre

If you are suffering from plantar fasciitis, start with simple home treatments: gentle massage, chilled bottle rolling, foot-strengthening exercises, comfortable footwear and appropriate support.

If your pain persists, returns repeatedly, or interferes with normal walking, arrange a podiatric assessment to identify the underlying cause.

Seek medical attention sooner if you have severe pain, significant swelling, redness, fever, numbness, an injury, or difficulty bearing weight.

Dubai Podiatry Centre

Helping patients understand their foot structure, improve their alignment and walk comfortably.

Website: www.dubaipodiatry.com

This article provides general educational information and does not replace an individual clinical assessment.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


Do your feet lean inward or outward when you stand or walk? Excessive inward rolling, known as overpronation, or outward rolling, known as supination, can affect foot alignment and pressure distribution. If you experience foot pain, heel pain or arch discomfort, a biomechanical assessment can help identify your individual support needs.

Watch our video to explore foot alignment and learn how custom-made corrective orthotics can support more comfortable standing and walking.


Custom Foot Orthotics at Dubai Podiatry Centre

At Dubai Podiatry Centre, we assess your foot mechanics and lower-limb alignment to prescribe custom orthotic insoles tailored to your feet. These individually prescribed devices are designed to support the arches, redistribute pressure and help control excessive foot movement.

For patients with symptomatic flat feet, overpronation or supination, custom foot orthotics may help reduce mechanical strain and improve comfort during everyday activities. Your podiatrist will assess whether orthotics are suitable for your symptoms and footwear.

Our Assessment and Orthotic Fitting Process

  • Registration and Consent
  • Consultation
  • Clinical Examination
  • Biomechanical Assessment
  • 3D Body Scanning
  • Photography
  • Gypsum Casting
  • Orthotic Manufacture
  • Fitting
  • Footwear Assessment
  • Final checks and adjustments

From the initial consultation to final fitting, each stage helps us tailor your corrective orthotics to your clinical needs. Footwear assessment and adjustments help ensure the insoles fit appropriately within suitable shoes.

Book a Biomechanical Assessment in Dubai

Looking for a podiatrist in Dubai for flat feet, inward or outward foot leaning, heel pain or arch discomfort? Contact Dubai Podiatry Centre to book a biomechanical assessment and discuss custom-made orthotics, arch support and footwear advice for more comfortable walking.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


Hard skin under one big toe is more than the other and it’s splitting like paper cuts.

When hard skin keeps coming back, look at why the skin is protecting itself

A common complaint we hear from patients is:

“I constantly get hard skin underneath my big toe. It splits and feels like little paper cuts. I use foot cream, file it and have the callus removed during pedicures, but it always comes back.”


When callus repeatedly develops in exactly the same place, simply removing the hard skin may not address the reason it is forming.

Callus is often the skin’s response to repeated pressure, shear and friction. The location and pattern of the callus can therefore provide useful clues about how forces are travelling through the foot.

A patient with painful, splitting callus

In this particular case, the patient had recurring hard skin underneath her big toe which frequently split, producing a painful sensation similar to paper cuts.

She had tried creams, regular filing and intensive callus removal at pedicure salons, but the problem continued to return.

She also had areas of callus beneath the ball of the foot, particularly underneath the second metatarsal head, as well as callus and a corn around the fifth metatarsal head.

She had also noticed that her feet seemed to be becoming broader.

What was particularly interesting was the difference between her two feet.

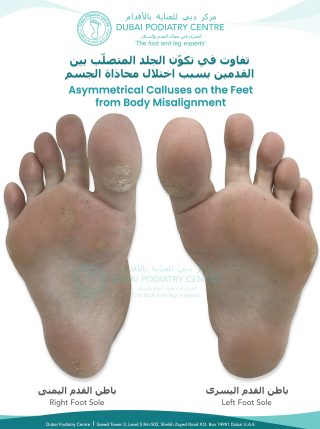
The left foot had only a relatively mild amount of hard skin underneath the big toe and forefoot.

The right foot showed considerably more.

Right and left foot soles showing uneven calluses and hard skin beneath the big toes, more pronounced on the right foot

Why was one foot worse than the other?

When we see a significant difference between the right and left feet, we don’t just examine the skin.

We look higher up the body.

In this patient’s assessment, we identified a leg-length discrepancy associated with pelvic asymmetry. Her right side demonstrated a pelvic tilt and altered lower-limb position, with the right foot abducting as she walked.

Instead of progressing straight over the big toe, she was repeatedly rolling across the side of it.

This created increased pressure and shear around the plantar and side of the big toe and first metatarsal region.

The skin was therefore repeatedly being subjected to mechanical stress in the same location.

Removing the callus could make the skin temporarily smoother, but it did not remove the forces that were causing it to develop.

The callus in the middle of the foot told us something different

Not every area of callus on this patient’s foot had the same mechanical explanation.

She also had callus underneath the second metatarsal head and around the fifth metatarsal head.

During her examination, this corresponded with changes in the shape and loading of her forefoot and a reduction in the normal transverse arch across the front of the foot.

As the forefoot spreads and its loading pattern changes, individual metatarsal heads can become more prominent beneath the foot.

The second metatarsal head is a particularly common area of increased plantar pressure.

Between the metatarsal bones and the ground lies an important layer of specialised fibrofatty tissue that helps cushion the foot.

When excessive pressure and shear repeatedly occur over a prominent metatarsal head, the skin may respond by producing additional keratin.

This is what we recognise as callus.

A more concentrated area of pressure can produce a corn.

Callus isn’t necessarily the problem. It can be a clue.

This is an important distinction.

Callus is not simply “dead skin that needs to be removed”

Its distribution can act almost like a map of pressure across the foot.


A podiatrist will therefore look at questions such as:

  • Is the callus symmetrical between the two feet?
  • Is it underneath a particular metatarsal head?
  • Is it underneath or along one side of the big toe?
  • Is there a corn in the centre of the callus?
  • Has the forefoot become broader?
  • Is one arch lower than the other?
  • Does one foot pronate more than the other?
  • Is one leg functionally or structurally longer?
  • Is there pelvic asymmetry?
  • Is the patient’s walking pattern creating excessive pressure or shear?


The position of the callus can help us understand what may be happening mechanically above it.

Why do some calluses crack and feel like paper cuts?

When callus becomes thick, it is less flexible than normal skin.

Every time the toe bends, twists or pushes against the ground, that thickened skin is subjected to movement and shear.

Eventually tiny fissures can develop.

These cracks can feel surprisingly painful, sometimes exactly like a paper cut.

Applying moisturiser may improve the flexibility and condition of the skin, and careful reduction of excessive callus can provide considerable relief.

However, if abnormal pressure and shear remain, the skin may continue to rebuild the callus.

That is why some patients find themselves in a cycle:

Callus forms → callus is filed or removed → skin feels better → the same mechanical forces continue → callus returns


What about people with diabetes or neuropathy?

This is particularly important in patients who have reduced sensation in their feet.

A person with neuropathy may not feel excessive pressure, rubbing, a blister or a developing wound normally.

Callus can itself be an important warning sign of repetitive high pressure, and in a neuropathic foot, areas beneath callus may be at increased risk of tissue breakdown and ulceration.

For this reason, recurrent callus in a person with diabetes, neuropathy or reduced circulation should not simply be aggressively filed or treated with corn-removing acids without appropriate professional assessment.


Why we examine the whole body

At Dubai Podiatry Centre, when we see a recurrent pattern of callus, particularly when one foot is significantly worse than the other, we don’t only look at the piece of hard skin.

We assess the biomechanics producing the pressure.

This can include examining:

Pelvis → hips → knees → ankles → subtalar joints → arches → forefoot → toes

Human bodies are naturally asymmetrical. Small differences are extremely common and do not necessarily cause problems.

It is when that asymmetry produces excessive or repetitive loading that symptoms can begin to appear.

In this patient’s case, the difference between the right and left callus patterns was an important clue.


Why the right and left orthotics may be different

If biomechanical assessment indicates that orthotic therapy is appropriate, the objective is not simply to put identical arch supports underneath both feet.

The two sides of the body may require different corrections.

For example, one orthotic may require a different thickness, inclination or degree of support from the other. The medial arch support may differ, and the forefoot or transverse arch may require different accommodation or correction.

The prescription is based on the individual patient’s examination.

The aim is to redistribute plantar pressure and improve lower-limb and foot mechanics so that the skin is no longer repeatedly exposed to the same excessive forces.


How long does it take for the callus to stop returning?

Skin does not necessarily change immediately when biomechanics are altered.

Even after the source of excessive pressure has been reduced, the skin may continue producing protective keratin for some time.

In clinical practice, we may see the callus pattern gradually reduce over the following months as pressure and shear are better controlled. For some patients, noticeable changes may occur over approximately four to six months, although this varies considerably according to the individual, their footwear, activity, skin condition and underlying biomechanics.

The important point is that we are not simply asking:

“How do we remove this hard skin?”

We are asking:

“Why does this particular piece of skin keep needing to protect itself?”

Once we understand that, we can work on the underlying mechanical cause as well as treating the skin itself.

The takeaway

Recurring callus can be more than a cosmetic problem.

Its location, shape and whether it is symmetrical between the two feet can provide valuable information about pressure, friction, foot structure and walking mechanics.

If the same callus keeps returning despite creams, filing and pedicures, it may be time to stop treating only the surface and investigate what is happening underneath it.

Dubai Podiatry Centre
Looking beyond the callus to understand why it formed.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


A big toenail that becomes white, lifted or separated along one side is often assumed to have a fungal infection. However, not every separated toenail is fungal.

In some patients, the underlying problem is mechanical and begins much further up the foot, at the alignment of the subtalar joint and ankle.

What causes the nail to separate?

When the foot pronates excessively, the subtalar joint and ankle lean inwards and the hallux, or big toe, can begin to internally rotate.

At the same time, the soft tissues and fibrofatty padding beneath the hallux are displaced laterally, towards the second toe.

Instead of remaining directly underneath the big toe, these tissues repeatedly move and press against the structures beneath and around the nail plate during standing and walking.

With thousands of steps each day, this repetitive movement can create an up-and-down and side-to-side mechanical force beneath the nail.

Over time, the nail plate can gradually be pulled away from the nail bed underneath. This produces a characteristic curved or U-shaped area of separation, particularly along the lateral border of the hallux nail.

This type of nail separation is known as onycholysis, but importantly, onycholysis describes the separation itself. It does not tell us what caused it.


An interesting left-versus-right comparison

This photographic example of the toes and feet provides an excellent example because the severity of the nail changes is different between the two feet.

On the left foot, the ankle/subtalar joint pronates approximately 30 degrees, and the lateral separation of the hallux nail plate is considerably greater.

On the right foot, the subtalar joint pronates approximately 12 degrees, and the lateral nail separation is noticeably less extensive.

The asymmetry is clinically interesting because the foot demonstrating the greater degree of pronation also demonstrates the greater degree of nail separation.

Rather than examining the toenail in isolation, we therefore need to examine what is happening to the whole foot, ankle and hallux during weight-bearing and walking.


Why can this be mistaken for fungal nail disease?

When air gets underneath a separated nail plate, the nail can appear white, yellowish or opaque. Debris may also accumulate beneath the separated portion.

Visually, this can resemble a fungal toenail.

However, treating a mechanically separated nail with antifungal treatment alone does not correct the forces repeatedly acting upon the nail.

Where fungal infection is suspected, appropriate clinical assessment and, when indicated, laboratory testing can help distinguish fungal nail disease from other causes of nail dystrophy and onycholysis.


The relationship with ankle alignment

In our clinical observations at Dubai Podiatry Centre, we frequently begin to see secondary foot and nail changes as subtalar joint pronation increases.

When inward deviation becomes more pronounced, mechanical stress upon the hallux can increase. With greater degrees of pronation, we may see progressively wider and deeper lateral nail separation together with increasing rotation or displacement of the hallux.

At very significant degrees of pronation, other structural changes, including hallux valgus, may also coexist.

These degree measurements should not be interpreted as universal diagnostic thresholds. Every patient is assessed individually because foot structure, joint mobility, footwear, activity, gait and other medical or dermatological factors can also influence the appearance of the toenail.

Treatment must address the cause, not simply the nail

If the separation is predominantly mechanical, our objective is to reduce the abnormal forces acting upon the hallux long enough for a healthier nail to grow forward while remaining attached to the nail bed.


Depending upon the individual assessment, treatment may include:

  • Corrective orthotics designed to improve subtalar joint alignment and reduce excessive pronation
  • Toe socks to encourage the toes to remain separated and in a more neutral position
  • Silicone toe liners or separators between the toes where appropriate to assist alignment
  • Footwear with an accommodating toe box, including suitable barefoot-style footwear where clinically appropriate, so that the toes are not compressed or displaced by the shoe

The important principle is consistency.

If a corrective device is worn for only one hour each day but the foot spends the remaining weight-bearing hours returning to its previous position, the mechanical forces responsible for the problem continue.

The objective is to maintain improved foot and toe alignment for as much of the patient’s weight-bearing day as reasonably possible.


How long does the nail take to recover?

Toenails grow slowly.

The recovery period therefore depends partly upon how far backwards the existing separation extends. The damaged portion cannot simply be pushed back onto the nail bed. Instead, we need to reduce the causative mechanical stress and allow healthier nail to gradually grow forward.

For some patients, visible improvement may occur over several months. A mechanically separated area may require approximately four to six months or longer to grow forward sufficiently, depending upon the depth of separation, individual nail-growth rate and how effectively the underlying mechanical problem is controlled.

Look beyond the toenail

A separated toenail does not always mean a fungal toenail.

Sometimes the toenail is simply showing us the end result of a biomechanical problem occurring elsewhere in the foot.

By examining the nail together with the hallux position, plantar soft tissues, subtalar joint, ankle alignment, gait and footwear, we can investigate why the nail is separating rather than treating its appearance alone.

Michelle Duffy Champlin
B.Sc. (Podiatry), M.Ch.S., S.R.Ch. (UK)
Chief Podiatrist
Dubai Podiatry Centre


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


Comparison of inward-leaning ankles without support, with accommodative insoles, and with corrective orthotics


Do your ankles roll inward when you stand or walk? You may have been advised to try insoles, but different types of foot support serve different purposes. Understanding the difference can help you ask the right questions during a podiatry assessment.

What Are Accommodative Insoles?

Accommodative insoles are generally soft and cushioned. They are designed to support the foot and relieve pressure on sensitive areas. They may improve comfort for people with tender soles or painful calluses, but cushioning alone does not necessarily address abnormal foot alignment.

What Are Corrective Orthotics?

Corrective, or functional, orthotics are designed to influence how the foot moves inside the shoe. For some people with flat feet or overpronation, a prescribed orthotic may help manage excessive inward rolling, support foot position and redistribute pressure while walking.

The image shows inward-leaning ankles alongside accommodative insoles and corrective orthotics. It illustrates the difference between cushioning the foot and providing support intended to guide its movement.

Which Type of Foot Support Is Right for You?

The choice depends on your symptoms, foot structure, walking pattern and footwear. A podiatrist can assess how your feet and ankles function before recommending accommodative insoles, custom corrective orthotics or another approach.

If you experience foot pain, heel pain, arch discomfort or recurring calluses, book a biomechanical foot assessment at Dubai Podiatry Centre. We will evaluate your foot alignment and walking mechanics to recommend support suited to your needs.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


Many people become frustrated when trying to treat a plantar wart. They may have tried over-the-counter salicylic acid, cryotherapy (freezing), or various home remedies, only to find that the wart stubbornly remains.

The reason is simple: not all warts behave in the same way.


Why Warts on the Feet Are Different

A wart on the back of the hand or another area of the body often appears as a small raised lump. This is because the skin in these areas is relatively thin and flexible, allowing the wart to grow outward.

The sole of the foot is completely different.

The skin on the bottom of the foot is much thicker and stronger because it is designed to withstand the pressure of standing and walking. Instead of growing outward, a plantar wart is compressed by body weight and becomes trapped beneath the thick outer layers of skin.

As a result, much of the wart lies within the skin rather than sitting prominently on top of it. This is why plantar warts often appear relatively flat while extending deeper into the skin layers.


Why Some Treatments Work Better on Hand Warts Than Plantar Warts

Because common warts on the hands are more exposed, superficial treatments such as:

  • Salicylic acid
  • Cryotherapy (liquid nitrogen freezing)
  • Occlusion methods

can often work very well.

However, plantar warts are protected by the thick skin of the sole. Treatments that work primarily on the surface may struggle to reach the full extent of the infected tissue beneath.

This is one reason why treatment of plantar warts can be slower and sometimes less predictable than treatment of warts elsewhere on the body.


Our Approach at Dubai Podiatry Centre

At Dubai Podiatry Centre, our goal is to make the wart more accessible to the body’s natural healing mechanisms.

Rather than aggressively destroying tissue, we focus on improving the quality and softness of the overlying skin. As the thick layers gradually become softer and thinner, the body is better able to recognise and respond to the viral infection.

The tiny black dots often seen within a plantar wart are small blood vessels that have become altered by the wart tissue. These blood vessels are part of the body’s normal circulation and immune surveillance system.


Why We Use Vitamin A

Vitamin A helps regulate normal skin cell turnover and supports healthy skin function.

We recommend applying Vitamin A cream to the plantar wart each evening and covering it with a non-absorbent dressing overnight.

Treatment is usually continued for approximately three skin cycles.

A skin cycle lasts around 28 days, meaning treatment is typically continued for 12–14 weeks.

During this period, the thick overlying skin gradually softens and normalises, allowing the body’s immune system to recognise and clear the viral tissue more effectively.

Many patients notice significant improvement during this timeframe.


What Is Dermojet Treatment?

For stubborn or longstanding plantar warts, we often combine Vitamin A therapy with Dermojet treatment.

The Dermojet uses a high-pressure microjet of local anaesthetic delivered through an opening smaller than a conventional needle.

The medication passes through the skin and disperses within the deeper tissue layers without the need for a traditional injection.

This creates a controlled healing response within the affected tissue while avoiding significant damage to the skin surface.

As healing occurs, the body’s immune system is stimulated within the wart tissue, helping to clear the virus.

In our clinical experience, the combination of Vitamin A therapy and Dermojet treatment provides some of the most successful outcomes for difficult plantar warts.


Why We Do Not Routinely Cut Out Plantar Warts

Many people assume that simply cutting out a plantar wart would solve the problem.

Unfortunately, plantar warts often extend beyond what is visible on the surface.

To completely remove all affected tissue surgically, a large and deep section of skin may need to be excised.

On the sole of the foot, this can result in:

  • Significant scar tissue formation
  • Persistent discomfort when walking
  • Hard callus formation
  • Long-term pressure-related problems

For these reasons, surgical excision is generally not our preferred treatment option.


Why We Do Not Routinely Use Cryotherapy on the Sole of the Foot

Cryotherapy can be effective for some types of warts, particularly those located on thinner skin.

However, on the sole of the foot it often requires multiple treatments and can be quite painful.

In our experience, the success rate is often lower than patients expect, particularly for deeply embedded plantar warts.

We are also cautious when considering cryotherapy around the toes because freezing treatments affect local blood circulation and can occasionally cause unnecessary tissue injury.


Our Recommended Treatment Plan

For most plantar warts, we recommend:

1. Daily Vitamin A application.
2. Occlusion with a non-absorbent dressing overnight.
3. Treatment continued for approximately 12–14 weeks.
4. Dermojet therapy for persistent or resistant lesions.

By helping the skin return to a healthier state and stimulating the body’s natural healing response, many plantar warts can be cleared without aggressive surgery or repeated freezing treatments.

If you are struggling with a plantar wart that simply won’t go away, a consultation with a podiatrist can help determine the most appropriate treatment plan for your particular case.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


When we think about the arches of our feet, most people immediately picture the large arch running along the inside of the foot.

But there is another, much smaller arch at the front of the foot that we pay very close attention to during a biomechanical assessment at Dubai Podiatry Centre.

It is called the transverse arch.


What is the transverse arch?

The front part of your foot is called the forefoot. It includes the toes and the metatarsal bones, which are the long bones immediately behind your toes.

Across the forefoot, just behind the toes where they connect with the foot, is the transverse arch.

Rather than running from the heel towards the toes like the more familiar medial arch, the transverse arch runs across the foot from side to side.

It is a relatively small arch, but biomechanically it can be extremely important.


What happens when the transverse arch starts to drop?

Over time, the forefoot can begin to spread and the transverse arch can become lowered.

We sometimes describe this to patients as the metatarsal bones beginning to “avalanche” forwards and downwards.

Although this change is occurring in a relatively small area at the front of the foot, it can influence the way the rest of the foot functions.

The metatarsal bones do not work independently from the remainder of the foot. They form part of the interconnected structure of the foot and contribute to its stability and function during standing and walking.

As the forefoot begins to change position, we may also see changes occurring through the larger medial arch, the midfoot and eventually the mechanics around the ankle.

This is why we never look at the transverse arch in isolation.


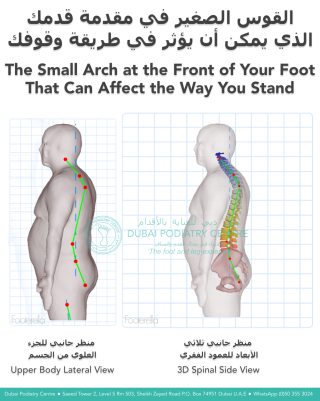
3D postural assessment showing how a collapsed forefoot transverse arch may affect standing posture and spinal alignment


Are you beginning to look hunched forwards?

One of the observations that can prompt us to investigate the forefoot is a change in a person’s stature.

Sometimes a patient, or their family, will say that they are beginning to “look hunchbacked” or that they appear to be leaning forwards.

The head may be sitting further forwards, the shoulders may appear more rounded and the person can develop an increasingly stooped appearance.

There are, of course, many different reasons why somebody may develop a forward head position or stooped posture. It should never automatically be assumed that it is coming from the feet.

However, it is one of the physical signs that makes us look more carefully at the person’s overall biomechanics.

We look at the person from the side and assess their stature. We look at the position of the head and shoulders. We observe how they stand and walk.

Then we investigate what is happening underneath them.

In particular, we examine the sole of the foot and the forefoot to see what has happened to the transverse arch.

If that small arch has dropped and the metatarsal bones have moved forwards and downwards, it may be contributing to a chain of biomechanical changes occurring further up the body.

Your feet form the foundation of your posture


The feet provide the foundation for the body when we stand and walk.

Changes in that foundation can sometimes contribute to compensations further up the biomechanical chain.

This is why a person’s posture can give us clues about what we should investigate in their feet.

A forward head, rounded shoulders, a stooped stance or a tendency to shuffle when walking does not diagnose a foot problem. However, these observations can be a reason to include the feet in the assessment rather than concentrating only on the upper body.

Sometimes the clue is visible at the shoulders and head, while part of the biomechanical problem may be much further down, at the sole of the foot.


Why we look for problems early

One of the reasons we pay such close attention to the transverse arch is that it can give us an opportunity to identify biomechanical changes relatively early.

If the transverse arch has started to lower but the remainder of the foot is still relatively well controlled, treatment can be much simpler.

Where appropriate, a custom corrective orthotic can be designed to support and lift the transverse arch and improve the mechanical stability of the forefoot.

The objective is not simply to put something soft underneath a painful area. It is to address the position and function of the forefoot as part of the mechanics of the entire foot.


What if the whole foot has already started to collapse?

More advanced biomechanical changes can also be managed. It simply requires a different approach.

If changes have progressed through the forefoot, midfoot and ankle, attempting to correct everything at once may not be appropriate or comfortable.

Instead, orthotic therapy may need to be carried out step by step and stage by stage.

We may initially need to address the forefoot and transverse arch. As the foot adapts, we can reassess the midfoot, medial arch, rearfoot, heel and ankle mechanics.

This process naturally takes longer than treating an early biomechanical change.

A small arch can give us a big clue

The transverse arch is a relatively small structure, but it can tell us a great deal about what is happening throughout the foot.

This is why we don’t assess feet simply by asking, “Where does it hurt?”

We look at the toes, forefoot, midfoot, heel and ankle. We look at how you stand. We look at the position of your shoulders and head. We watch how you walk.

If somebody tells you that you are beginning to look more hunched over, or you notice that your head is increasingly sitting forwards and your shoulders are becoming rounded, there can be many possible explanations.

But don’t forget to look down.

A biomechanical assessment of the feet, and particularly that small transverse arch underneath the forefoot, may provide another important piece of the puzzle.

The earlier we identify a change in foot biomechanics, the easier it may be to manage before it progresses further.


Dubai Podiatry Centre
Biomechanical Foot Assessment and Custom Orthotic Therapy


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


A very small area of sudden, intense and highly localised pain in the sole of the foot can sometimes be caused by a foreign object embedded in the skin.

Because we put our full body weight through our feet, even something incredibly small—a tiny splinter, hair or fragment of glass—can become surprisingly painful. Patients will often describe being able to point to one exact spot that feels extremely sharp or painful when they stand or walk.


Even a Hair Can Become a Foreign Body

One of the more unusual foreign bodies we occasionally encounter is human hair.

For example, when someone shaves in the shower, freshly cut hairs can have extremely sharp ends. At the same time, warm water temporarily softens the outer layers of skin on the feet.

A short, stiff piece of freshly cut hair can occasionally penetrate this softened skin. With continued walking and pressure, it may gradually work deeper into the skin.

This can also occur with cat or dog hairs, particularly short, coarse hairs that can behave almost like tiny splinters.

Initially, the person may notice very little. However, as the foreign material penetrates more deeply and the surrounding tissue becomes inflamed, a very small area can become disproportionately painful.


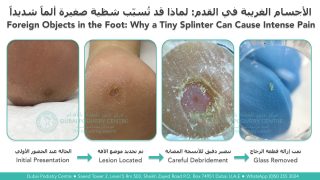
Glass splinter removed from the sole of the foot following assessment and careful debridement at Dubai Podiatry Centre


Why Does It Become So Painful?


The body recognises an embedded object as something that does not belong there and produces an inflammatory response around it. Occasionally, a small collection of pus may develop around the foreign material.

In other areas of the body, this may eventually drain spontaneously and allow the foreign body to escape.

The sole of the foot, however, has particularly thick, strong skin designed to withstand enormous amounts of pressure and friction. This can make spontaneous drainage more difficult.

Instead, the foreign object may remain trapped while every step continues to push pressure through the affected area.

The result can be intense pain concentrated within a surprisingly tiny area.


Common Foreign Objects We Find in Feet

Foreign bodies can enter the feet in many everyday situations. These include:

  • Tiny wooden splinters from gardening, decking or wooden floors
  • Small fragments of broken glass
  • Human hair following shaving
  • Coarse cat or dog hairs
  • Thorns and plant material
  • Small fragments picked up while walking barefoot outdoors
  • Splinters from harbour or marina decking
  • Sea urchin spines

Walking barefoot around swimming pools, gardens, beaches, marinas and decking areas can increase the opportunity for tiny objects to enter the skin.

Look Closely at the Area

Sometimes there is very little to see from the surface.

You may notice a tiny dark or discoloured area beneath the skin. Occasionally patients describe seeing a greenish or grey shadow, although colour alone cannot confirm that a foreign body is present.

One simple trick is to take a close-up photograph with your mobile phone in good lighting and enlarge the image. Modern phone cameras can sometimes reveal a tiny entry point or object that is difficult to see with the naked eye.

However, if you cannot easily see and grasp the object at the surface, repeatedly digging into the foot at home can make matters worse.

Sea Urchin Spines

Sea urchin injuries are usually much easier for the patient to recognise because they occur immediately after standing on or brushing against a sea urchin.

The difficulty is that sea urchin spines are fragile and can break, leaving fragments embedded beneath the skin.

At Dubai Podiatry Centre, we use careful podiatric techniques to access suitable superficial retained fragments and remove them while trying to avoid breaking the spine or driving it further into the tissues.

Deeply embedded fragments, significant swelling, persistent pain or suspected involvement of deeper structures may require further medical assessment or imaging.

Don’t Keep Digging at the Foot

One of the most important pieces of advice is not to repeatedly cut, squeeze or dig into the sole of the foot yourself.

If a foreign body is clearly protruding from the surface and can be removed easily, that may be straightforward. But when an object has disappeared beneath the skin, trying to find it with needles, blades or other instruments can push it deeper, introduce bacteria and cause additional tissue damage.

If you have a very small, intensely painful area on the foot—particularly after walking barefoot—and you cannot see what is causing it, a podiatrist can examine the area carefully.


When Should You Seek Medical Attention?


Seek professional assessment if the pain is increasing, you cannot comfortably walk, the object appears deeply embedded, or you develop redness, warmth, swelling, pus, bleeding or spreading inflammation.

People with diabetes, poor circulation, reduced sensation in the feet or impaired immunity should avoid attempting to remove embedded foreign bodies themselves and should seek professional assessment promptly.

Sometimes the tiniest object can cause an extraordinary amount of pain in the foot. Finding and safely removing the cause can provide enormous relief.

Dubai Podiatry Centre
Dubai, UAE
Specialist assessment and treatment of foot and lower-limb conditions.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


Plantar fasciitis is one of the most common causes of heel and arch pain. A typical symptom is pain underneath the heel when you first get out of bed in the morning, or when you stand up after sitting at your desk, driving or relaxing for a period of time.

The plantar fascia is a strong band of connective tissue running along the sole of the foot from the heel towards the forefoot. It plays an important role in supporting the arch and stabilising the foot during standing and walking.

When the plantar fascia is repeatedly placed under excessive tensile stress, particularly where it attaches to the calcaneus (heel bone), the area can become painful and irritated.

Importantly, plantar fasciitis is not always simply a problem with the plantar fascia itself. Foot and lower-limb biomechanics can contribute to excessive loading of the fascia. This is why successful treatment should aim not only to settle the painful area, but also to identify and reduce the mechanical stresses that are causing it.

Here are some simple measures that can be carried out at home.


1. Contrast Foot Baths – Warm and Cool Water Therapy

Contrast bathing can be a useful part of a home-care routine.

Prepare two containers deep enough for the water to reach approximately midway up the lower legs.

Warm bath: approximately 40–42°C
Cool bath: approximately 22°C

Place both feet and lower legs into the warm water for approximately one minute.

Then transfer them into the cool water for one minute.

Continue alternating between the warm and cool water, repeating the process approximately five times. The complete treatment should take around 10–12 minutes.

The change in temperature produces alternating warming and cooling of the tissues and changes in local blood flow. Many patients find this soothing, particularly towards the end of the day.

We generally recommend doing contrast bathing in the latter part of the day rather than immediately before going to bed, as some people find the treatment quite stimulating.

Always check the temperature carefully before immersing your feet. Contrast bathing may not be appropriate if you have reduced sensation, neuropathy, vascular disease, diabetes-related foot complications or another condition affecting your ability to accurately feel temperature.


2. Massage the Plantar Fascia with Cork Balls

Cork balls are an excellent and simple way of gently massaging the sole of the foot while sitting at home or at your desk.

Different-sized cork balls can be used for different areas of the foot.

With a small cork ball, place the ball underneath the heel while seated and gently rest the foot over it. Make small circular movements around the plantar heel, alternating between clockwise and anticlockwise movements.

A medium or larger cork ball can be placed underneath the arch. Gently roll the foot backwards and forwards over the ball to massage the plantar fascia and surrounding soft tissues.

This is particularly useful if you spend long periods sitting.

One of the characteristic symptoms of plantar fasciitis is pain when standing after rest. Gentle movement and massage before standing can help prepare the foot for loading again.

The massage should feel comfortable rather than painful. Aggressive rolling directly over an acutely painful heel is unnecessary and can aggravate already sensitive tissue.


3. Plantar Fascia Support Tape

Traditional plantar fascia taping often involves applying several individual strips of tape underneath and around the foot. Although this can be effective, it can also be cumbersome and difficult for patients to apply themselves.

A purpose-designed single plantar fascia support tape can be a much simpler home option.

The tape is only a few millimetres thick and can provide gentle padding underneath the foot while helping to reduce some of the tensile load placed upon the plantar fascia.

It is generally worn during the daytime, when the foot is weight-bearing and the plantar fascia is repeatedly being loaded.

Taping is not intended to permanently correct the underlying biomechanics. Instead, think of it as temporary mechanical assistance while the irritated tissue is recovering.


4. Support the Arch and Correct Excessive Foot Movement

If plantar fasciitis continues to return, it is important to look at why the plantar fascia is being overloaded.

The plantar fascia does not work independently from the rest of the foot and leg.

For example, excessive movement through the subtalar joint and lowering of the arch can increase the mechanical demands placed upon the plantar fascia. Changes in the forefoot and transverse arch may also affect the way the foot loads during walking.

When the foot is not functioning efficiently, the plantar fascia may be subjected to increased tension as it contributes to supporting and stabilising the foot.

This is why a suitable supportive insole or individually prescribed corrective foot orthotic can be extremely beneficial for some patients.

The purpose is not simply to cushion the painful heel. A properly selected device should address the mechanical forces contributing to the problem and reduce unnecessary tensile stress through the plantar fascia.

For patients with significant biomechanical abnormalities, a professional assessment is advisable rather than simply purchasing a very soft heel cushion.


5. Give Your Toes Enough Space

Footwear is another important part of plantar fasciitis management.

The toes are designed to spread and function as part of the foot’s natural support system. Constantly squeezing them together inside narrow or pointed footwear can interfere with normal forefoot mechanics.

We often recommend toe socks combined, where appropriate, with very soft silicone toe aligners to allow the toes to sit in a more natural position.

These can be combined with an orthotic incorporating appropriate arch and transverse-arch support.

The shoe itself should have sufficient width through the toe box to allow the toes to open rather than compressing them together.

For some patients, a wider, foot-shaped or barefoot-style toe box can be very helpful. However, footwear needs to be selected according to the individual foot and the stage of recovery; a sudden transition into very flexible or minimally cushioned footwear may not be appropriate during an acutely painful episode.


Dubai Podiatry Centre infographic showing home treatment options for plantar fasciitis, including cork-ball massage, plantar fascia support tape, corrective orthotics, toe aligners and toe socks


How Long Does Plantar Fasciitis Take to Heal?

This is one of the most important things to understand.

Plantar fasciitis rarely disappears overnight.

The plantar fascia is a very strong, highly loaded structure, and the attachment at the heel is repeatedly stressed every time you stand and walk.

Even when the underlying mechanical problem is being corrected and the symptoms begin to improve, it can take several months for the area to settle fully. In many of the patients we treat, we advise allowing approximately three to four months for progressive recovery, although individual healing times vary.

The key is consistency.

Contrast bathing, gentle cork-ball massage, plantar fascia support taping, appropriate footwear and correctly prescribed arch support can all work together to reduce stress on the painful area while the tissues recover.

Don’t Just Treat the Heel – Find Out Why It Hurts

Perhaps the most important message is that plantar fasciitis should not always be viewed simply as an isolated painful heel.

Persistent plantar fascia pain can be a sign that the foot is compensating for a wider biomechanical issue.

The position and movement of the forefoot, arch, subtalar joint, ankle, knee, pelvis and hip can all influence how forces are transmitted through the foot.

If your plantar fasciitis keeps returning, is becoming progressively worse, or has not improved despite appropriate home treatment, it is worth having your walking pattern and lower-limb biomechanics professionally assessed.

At Dubai Podiatry Centre, we assess the foot as part of the complete lower-limb mechanical system. By identifying why the plantar fascia is being overloaded, treatment can be directed towards both relieving the painful tissue and reducing the mechanical stresses that contributed to the problem in the first place.

Dubai Podiatry Centre
Helping your feet function better from the ground up.

This article provides general educational information and is not a substitute for individual medical assessment. Persistent or severe heel pain, swelling, neurological symptoms, inability to bear weight, or pain following an injury should be professionally assessed.


For more information or to book an appointment please call our clinic +971 4 3435390 or WhatsApp +971 50 3553024


Copyright Dubai Podiatry 2026. All rights reserved.

WhatsApp us